
Cardiovascular diseases are the leading cause of mortality in Spain, yet there is no systematic population-based cardiovascular screening program. This study evaluated the feasibility of a nurse-led, single-visit cardiovascular screening program in primary care (PreveCardio), and identified the prevalence of modifiable cardiovascular risk factors, their associated socioeconomic factors, and the translation of pilot findings into regional health policy.
MethodsWe conducted a cross-sectional study across 42 primary care centers in a Spanish region (January-March 2023). A random sample of 8491 individuals aged 50 to 75 years was invited to participate. Trained nurses performed a single 30-minute visit with point-of-care measurements (blood pressure, lipid profile, HbA1c) and validated questionnaires. Multivariable logistic regression models were fitted with Benjamini-Hochberg correction.
ResultsA total of 3545 individuals participated (41.8%; mean age 61.2±7.3 years; 56.7% women). The completeness of clinical data exceeded 99%. Elevated blood pressure was identified in 40.4%, obesity in 29.5%, nonoptimal low-density lipoprotein cholesterol in 48.7%, prediabetes in 30.7%, and active smoking in 19.5%. Smoking showed the steepest socioeconomic gradient (aOR, 3.25; 95%CI, 2.09-5.03). The direct cost per participant was €11.75.
ConclusionsA nurse-led, single-visit cardiovascular screening program is operationally feasible in Spanish primary care, revealing a high burden of modifiable cardiovascular risk factors and significant socioeconomic disparities. Smoking showed the steepest income-associated gradient. This pilot study led to the approval of the first systematic cardiovascular screening program in a Spanish autonomous community.
Keywords
Abbreviations
Cardiovascular diseases remain the leading cause of mortality in Spain, accounting for approximately 29% of all deaths, and represent a substantial economic and health care burden for the publicly-funded health system.1,2 The 2021 European Society of Cardiology (ESC) guidelines on cardiovascular disease prevention recommend systematic cardiovascular risk assessment every 5 years for men aged over 40 and women aged over 50, with the aim of identifying individuals harboring modifiable risk factors amenable to early intervention.3
Several European countries have implemented population-based cardiovascular screening programs in primary care. The NHS Health Check in England invites over 3.5 million adults aged 40 to 74 years annually for structured assessment of cardiovascular disease risk, type 2 diabetes, and dementia.4,5 Italy's CARDIO50 program targets adults at age 50 years for a single preventive visit, and this model has been adapted through the European Commission's YOUNG50 project, which piloted sites in Luxembourg, Romania, and Lithuania.6,7 Nordic countries have integrated systematic cardiovascular risk assessment into primary care through various approaches.8 In Spain, however, none of the 17 autonomous communities operates a systematic population-based cardiovascular screening program, and prevention relies largely on opportunistic approaches linked to routine medical consultations. Unlike opportunistic screening, which depends on individuals attending primary care for other reasons, a systematic population-based program actively invites a random sample from the health card registry, an approach not yet implemented in any Spanish autonomous community.9,10
This context raises a policy question of considerable importance: whether a cardiovascular screening program is feasible, affordable, and capable of generating data of sufficient quality to inform regional implementation decisions within the Spanish primary care framework. To address this question, a collaborative network of hospitals, primary care centers, and the emergency medical service in a Spanish region launched the pilot program for adults aged 50 to 75 years.
The aims of this study were: a) to evaluate the feasibility of the program (participation rate, data completeness, direct costs); b) to identify the prevalence of modifiable cardiovascular risk factors (CVRF) and their socioeconomic associations as indicators of the program's clinical value and to inform equitable implementation; and c) to document the translation of pilot findings into regional health policy.
METHODSStudy design and settingThis was a cross-sectional study conducted between January and March 2023 across 42 primary care centers belonging to a collaborative health care network in a Spanish region. The network covers approximately 1 million people across 4 health areas with diverse socioeconomic profiles: an urban area (area A: 13 centers, n=1195 participants), and 3 peripheral areas (area B: 12 centers, n=896; area C: 8 centers, n=711; area D: 9 centers, n=743). All PreveCardio collaborators are listed in the supplementary data. The study is reported following the STROBE guideline for cross-sectional observational studies.11
ParticipantsThe sample size was calculated a priori for population proportion estimation under maximum-variance assumptions, with a 95% confidence level, yielding a target of 3419 evaluable participants. To accommodate an anticipated participation rate of approximately 40% (consistent with European preventive screening programs, typically 40-50%) and additional losses from unreachable registry contacts (incorrect addresses, deceased individuals, recent registry changes), a sampling frame of 8491 individuals aged 50 to 75 years was generated through stratified random sampling from the public health card registries of the 42 participating centers in 2022 (registered population 981 686), with allocation proportional to center size, irrespective of prior cardiovascular disease history. This age range was selected for its alignment with European screening initiatives such as the CARDIO50 program and because it represents a demographic group with sufficient baseline cardiovascular risk to efficiently evaluate program feasibility. Invitations were sent by postal letter followed by up to 3 telephone calls. Owing to the temporal lag between cohort generation and the clinical visit, 65 participants had aged to 76 to 77 years by the time of screening and were retained in the analytical sample.
Data collectionAll data were collected during a single 30-minute visit conducted by trained nurses (n=127) following standardized protocols. Objective measurements included resting blood pressure (single measurement; repeated during the same visit when the initial reading was elevated), weight, and height. A capillary blood sample was obtained for point-of-care analysis of the lipid profile (total cholesterol, high-density lipoprotein cholesterol, low-density lipoprotein cholesterol [LDL-C] cholesterol, triglycerides) and glycated hemoglobin (HbA1c). Participants were instructed to fast for 6hours before their appointment.
Self-reported data included prior physician-diagnosed hypertension, dyslipidemia, diabetes mellitus, and atherosclerotic cardiovascular disease (ACVD), as well as current smoking status. Physical activity was assessed using the Rapid Assessment of Physical Activity questionnaire (RAPA 1).12 Alcohol consumption was measured in standard units with sex-specific thresholds per Ministry of Health guidelines.13 Mediterranean diet adherence was evaluated with the validated 14-item PREDIMED questionnaire.14 Socioeconomic status was assessed through self-reported household income (5 categories: <1100; 1100-1800; 1801-2700; 2701-3900;> 3900 €/mo), educational level, employment status, and country of origin, using instruments from the Spanish National Statistics Institute and the Centre for Sociological Research.15,16
Ten-year cardiovascular risk was estimated using SCORE2 for participants aged 50 to 69 years and SCORE2-OP for those aged 70 to 77 years, using the published algorithms for low-risk countries (Spain), based on age, sex, systolic blood pressure, total and high-density lipoprotein cholesterol as separate predictors, and smoking status.3 Risk was classified as low, moderate, or high according to ESC 2021 age-specific thresholds. Nurses received structured in-person training at 4 sites, supplemented by instructional videos and study guides. A central research team of 4 members was available throughout data collection. An electronic data collection system with range validation was designed, and participants with abnormal findings were referred to their primary care physician. During the visit, nurses provided individualized lifestyle recommendations based on the participants’ results and delivered an informational leaflet on cardiovascular risk factors. Smokers willing to quit were offered referral to smoking cessation services.
Variable definitionsElevated blood pressure was defined as systolic blood pressure ≥ 140 mmHg or diastolic blood pressure ≥ 90 mmHg (single measurement; see limitations section). Obesity was defined as body mass index (BMI) ≥ 30 kg/m2. Nonoptimal LDL-C was defined as ≥ 55mg/dL for participants with known ACVD or ≥ 116mg/dL for those without, in accordance with ESC guidelines.3 Prediabetes was defined as HbA1c 5.7%-6.4% and new-onset diabetes as HbA1c ≥ 6.5% without prior diagnosis. For the analysis of accumulated risk factor burden, dysglycemia was defined as HbA1c ≥ 5.7% (prediabetes or new-onset diabetes combined). Active smoking was defined as current regular consumption. Physical inactivity was defined as not meeting ≥ 150min/wk of moderate or ≥ 75min/wk of vigorous activity. Risky alcohol intake was defined as> 2 standard drinks/d for men or> 1 for women.13
Statistical analysisContinuous variables are presented as mean±standard deviation. Categorical variables are reported as absolute frequencies, percentages, and 95% confidence intervals (95%CI) for primary prevalence estimates. Comparisons across health areas were performed using the chi-square test or Fisher exact test for categorical variables, with Benjamini-Hochberg (BH) correction for false discovery rate in multiple comparisons.17
The primary analysis of associated socioeconomic factors was performed using multivariable logistic regression models. For each CVRF (binary dependent variable), a model was fitted including age (continuous), sex, health area (4 categories; reference: area A), educational level (3 categories: low, intermediate, high; reference: high), household income (5 categories; reference:> €3900/mo), and country of origin (3 categories: Spain, Latin America, Other; reference: Spain) as covariates. Adjusted odds ratios (aOR) with 95%CI and exact P-values are reported.
The trend association between income and each risk factor was assessed through ordinal trend tests, entering income as a continuous ordinal variable in logistic regression models. The OR per income category increase with 95%CI is reported.18
Benjamini-Hochberg correction was applied; P <.05 was considered statistically significant. Sensitivity analyses included modified Poisson regression with robust variance and cluster-robust standard errors for center-level clustering.
Missing data analysis showed that the primary clinical variables had completeness exceeding 99%. Household income was the variable with the highest proportion of missing data (16.0%), corresponding to refusals or uncertainty. The characteristics of participants with and without income data were compared to assess the pattern of missingness. Primary regression analyses were conducted in 2800 to 2963 participants with complete data on income and outcome; the exact sample size (n) varied by outcome because of outcome-specific missing values, notably for LDL-C (n=2800). As a sensitivity analysis, we performed multiple imputation (m=5) using chained equations (MICE) to assess the robustness of the findings to missing income data.
To assess whether socioeconomic associations were modified by age, each multivariable model was extended with an interaction term between continuous age (centered at the sample median, 60 years) and household income (ordinal, 1-5). Likelihood-ratio tests (1 df) were applied across the 8 CVRF with Benjamini-Hochberg correction. For outcomes with significant interaction, income gradients were estimated separately in participants aged <60 and ≥ 60 years.
Analyses were performed with Python 3.12 (statsmodels, scipy, pandas).
EthicsThe study was approved by the Clinical Research Ethics Committee of Hospital Clínico San Carlos, Madrid, Spain (code 22/237-E). All participants provided written informed consent. The study was conducted in accordance with the principles of the Declaration of Helsinki.
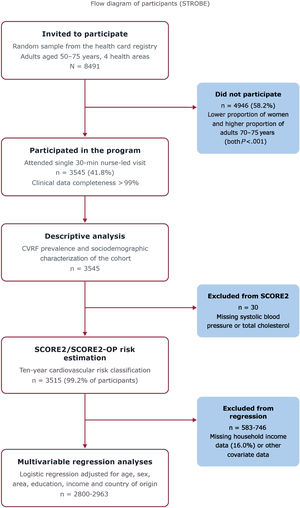
RESULTSParticipation and data completenessOf 8491 individuals invited, 3545 participated (41.8%; figure 1). Clinical data completeness exceeded 99% for the SCORE2 input variables (30 participants were excluded due to zero values in systolic blood pressure or total cholesterol, indicating measurement errors). A total of 2800 to 2963 participants had complete data for all regression covariates (16.0% missing income data). Participants without income data were more likely to be women (61.9% vs 55.7%, P=.007) and had a slightly lower prevalence of elevated blood pressure (36.1% vs 41.2%, P=.024), with no significant differences in age, obesity, or smoking prevalence (table S1), suggesting that data were not missing completely at random.

STROBE flow diagram of participants. Of 8491 individuals invited (random sample, age 50-75 years, 4 health areas), 4946 (58.2%) did not participate. A total of 3545 (41.8%) participated, all linked for analysis (clinical data completeness> 99%). The regression analysis included 2800 to 2963 participants with complete data for all covariates (16.0% missing income data). CVRF, cardiovascular risk factors; SCORE2/SCORE2-OP, Systematic Coronary Risk Evaluation (2/Older Persons); STROBE, Strengthening the Reporting of Observational Studies in Epidemiology.
Compared with participants, nonparticipants included a lower proportion of women (51.9% vs 56.7%; P <.001) and a higher proportion of individuals aged 70 to 75 years (17.3% vs 13.6%; P <.001; table S2).
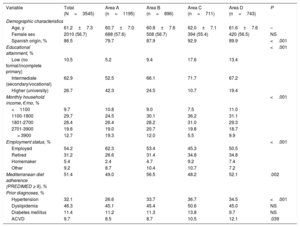
Participant characteristicsThe mean age was 61.2±7.3 years, and 56.7% were women (table 1). Significant geographic variation was observed in educational attainment, with 42.3% university-educated participants in area A compared with 10.7% in area C (P <.001). Income distribution also varied significantly among areas (P <.001), with area A concentrating the highest proportion in the upper income categories. The population was predominantly of Spanish origin in area C (92.9%) with greater diversity in area A (79.7%). Mediterranean diet adherence (PREDIMED score ≥ 9) was highest in area B (56.5%) and lowest in area C (48.2%). Self-reported atherosclerotic cardiovascular disease (ACVD) was present in 9.7% (95%CI, 8.8-10.7) of participants, ranging from 8.5% in area A to 12.1% in area D (P=.039).
Baseline characteristics of participants by health care area
| Variable | Total (N=3545) | Area A (n=1195) | Area B (n=896) | Area C (n=711) | Area D (n=743) | P |
|---|---|---|---|---|---|---|
| Demographic characteristics | ||||||
| Age, y | 61.2±7.3 | 60.7±7.0 | 60.8±7.6 | 62.0±7.1 | 61.6±7.6 | – |
| Female sex | 2010 (56.7) | 688 (57.6) | 508 (56.7) | 394 (55.4) | 420 (56.5) | NS |
| Spanish origin, % | 86.5 | 79.7 | 87.9 | 92.9 | 89.9 | <.001 |
| Educational attainment, % | <.001 | |||||
| Low (no formal/incomplete primary) | 10.5 | 5.2 | 9.4 | 17.6 | 13.4 | |
| Intermediate (secondary/vocational) | 62.9 | 52.5 | 66.1 | 71.7 | 67.2 | |
| Higher (university) | 26.7 | 42.3 | 24.5 | 10.7 | 19.4 | |
| Monthly household income, €/mo, % | <.001 | |||||
| <1100 | 9.7 | 10.8 | 9.0 | 7.5 | 11.0 | |
| 1100-1800 | 29.7 | 24.5 | 30.1 | 36.2 | 31.1 | |
| 1801-2700 | 28.4 | 26.4 | 28.2 | 31.0 | 29.3 | |
| 2701-3900 | 19.6 | 19.0 | 20.7 | 19.8 | 18.7 | |
| > 3900 | 12.7 | 19.3 | 12.0 | 5.5 | 9.9 | |
| Employment status, % | <.001 | |||||
| Employed | 54.2 | 62.3 | 53.4 | 45.3 | 50.5 | |
| Retired | 31.2 | 26.6 | 31.4 | 34.8 | 34.8 | |
| Homemaker | 5.4 | 2.4 | 4.7 | 9.2 | 7.4 | |
| Other | 9.2 | 8.7 | 10.4 | 10.7 | 7.2 | |
| Mediterranean diet adherence (PREDIMED ≥ 9), % | 51.4 | 49.0 | 56.5 | 48.2 | 52.1 | .002 |
| Prior diagnoses, % | ||||||
| Hypertension | 32.1 | 26.6 | 33.7 | 36.7 | 34.5 | <.001 |
| Dyslipidemia | 46.3 | 45.1 | 45.4 | 50.6 | 45.0 | NS |
| Diabetes mellitus | 11.4 | 11.2 | 11.3 | 13.8 | 9.7 | NS |
| ACVD | 9.7 | 8.5 | 8.7 | 10.5 | 12.1 | .039 |
ACVD, atherosclerotic cardiovascular disease.
The data are expressed as No. (%) or mean±standard deviation.
Education categories: low (no formal/incomplete primary), intermediate (secondary/vocational), higher (university degree). Education percentages are calculated on the 3500 participants with valid data. Income percentages are calculated on the 2978 participants with valid data.
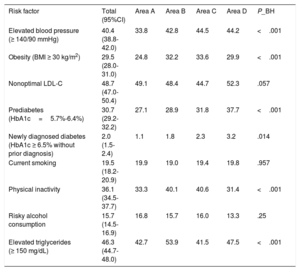
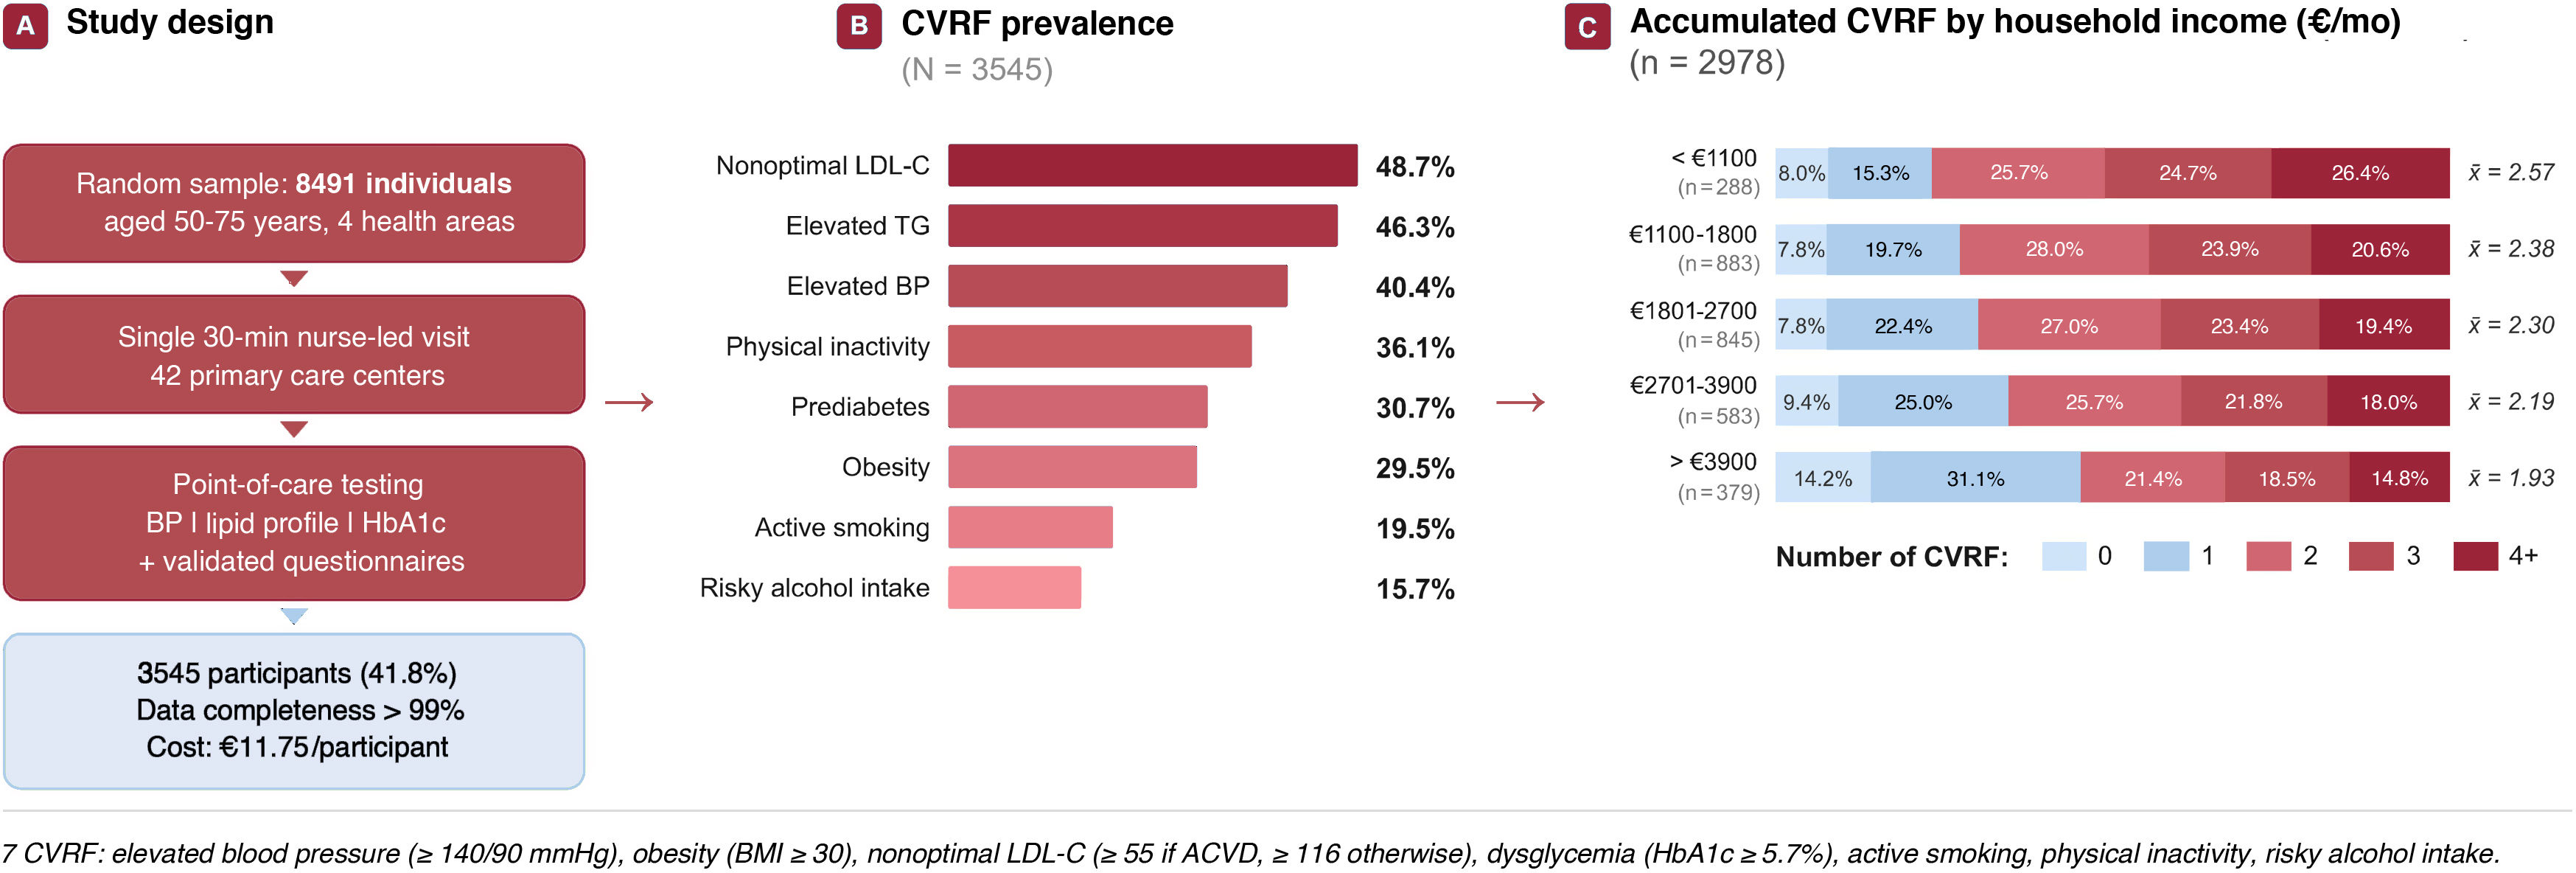
A high burden of modifiable CVRF was observed (table 2; figure 2). Elevated blood pressure (≥ 140/90 mmHg) affected 40.4% (95%CI, 38.8-42.0) of participants. Obesity affected 29.5% (95%CI, 28.0-31.0). Nonoptimal LDL-C was present in 48.7% (95%CI, 47.0-50.4) without significant geographic variation after BH correction (P_BH=.057). Prediabetes (HbA1c, 5.7-6.4%) affected 30.7% (95%CI, 29.2-32.2). New-onset diabetes (HbA1c ≥ 6.5% without prior diagnosis) was detected in 2.0% (95%CI, 1.5-2.4).
Prevalence of cardiovascular risk factors by health care area
| Risk factor | Total (95%CI) | Area A | Area B | Area C | Area D | P_BH |
|---|---|---|---|---|---|---|
| Elevated blood pressure (≥ 140/90 mmHg) | 40.4 (38.8-42.0) | 33.8 | 42.8 | 44.5 | 44.2 | <.001 |
| Obesity (BMI ≥ 30 kg/m2) | 29.5 (28.0-31.0) | 24.8 | 32.2 | 33.6 | 29.9 | <.001 |
| Nonoptimal LDL-C | 48.7 (47.0-50.4) | 49.1 | 48.4 | 44.7 | 52.3 | .057 |
| Prediabetes (HbA1c=5.7%-6.4%) | 30.7 (29.2-32.2) | 27.1 | 28.9 | 31.8 | 37.7 | <.001 |
| Newly diagnosed diabetes (HbA1c ≥ 6.5% without prior diagnosis) | 2.0 (1.5-2.4) | 1.1 | 1.8 | 2.3 | 3.2 | .014 |
| Current smoking | 19.5 (18.2-20.9) | 19.9 | 19.0 | 19.4 | 19.8 | .957 |
| Physical inactivity | 36.1 (34.5-37.7) | 33.3 | 40.1 | 40.6 | 31.4 | <.001 |
| Risky alcohol consumption | 15.7 (14.5-16.9) | 16.8 | 15.7 | 16.0 | 13.3 | .25 |
| Elevated triglycerides (≥ 150 mg/dL) | 46.3 (44.7-48.0) | 42.7 | 53.9 | 41.5 | 47.5 | <.001 |
95%CI, 95% confidence interval; BMI, body mass index; BP, blood pressure; LDL-C, low density lipoprotein cholesterol; P_BH, P-value after Benjamini-Hochberg correction.
Unless otherwise indicated, the data are expressed as percentages.
Nonoptimal LDL-C was defined as ≥ 55mg/dL with known ACVD or ≥ 116mg/dL without ACVD.

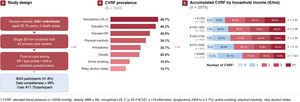
Central illustration. Graphical summary of the PreveCardio pilot program: a cross-sectional study in 42 primary care centers. Of 8491 individuals invited to participate (aged 50-75 years), 3545 participated (41.8%) in a single 30-minute visit with point-of-care testing. There was a high prevalence of modifiable cardiovascular risk factors (CVRF); the largest socioeconomic disparity was smoking (adjusted odds ratio 3.25 for the lowest income category) and CVRF accumulation followed an income gradient (mean 2.57 vs 1.93). Dysglycemia: HbA1c ≥ 5.7%. CVRF, cardiovascular risk factors; HbA1c, glycated hemoglobin.
Active smoking was reported by 19.5% (95%CI, 18.2-20.9) without significant area variation (P_BH=.957). Physical inactivity affected 36.1% (95%CI, 34.5-37.7). Risky alcohol intake was reported by 15.7% (95%CI, 14.5-16.9). Elevated triglycerides (≥ 150mg/dL) were present in 46.3% (95%CI, 44.7-48.0).
Significant geographic variation after BH correction was observed for elevated blood pressure, obesity, new-onset diabetes, prediabetes, physical inactivity, and elevated triglycerides (all P_BH<.05; table 2), while nonoptimal LDL-C, active smoking, and risky alcohol intake did not vary significantly among areas (table 2).
Cardiovascular risk classification using SCORE2 (ages 50-69 years, n=2879) and SCORE2-OP (ages 70-77 years, n=636) revealed marked sex and age differences in cardiovascular risk distribution; overall, 40.1% of screened adults aged 50 to 77 years were at moderate or high 10-year cardiovascular risk (table S3).
When 7 CVRF were counted per participant (elevated blood pressure, obesity, nonoptimal LDL-C, dysglycemia [HbA1c ≥ 5.7%], active smoking, physical inactivity, and risky alcohol intake), a monotonic income gradient in risk factor burden emerged (figure 2; table S4): mean accumulated CVRF decreased from 2.57 in the lowest income category (< 1100 €/mo) to 1.93 in the highest (> 3900 €/mo); 26.4% of participants in the lowest bracket had 4 or more CVRF compared with 14.8% in the highest.
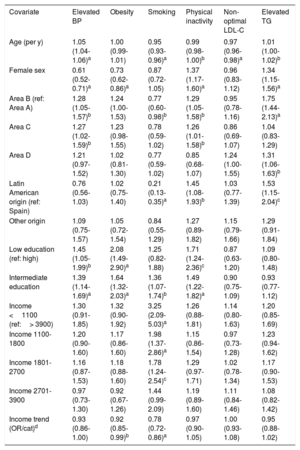
Independently associated socioeconomic factorsMultivariable logistic regression analysis (n=2800-2963) identified significant independent associations between socioeconomic indicators and CVRF, to be interpreted as cross-sectional associations rather than causal effects (table 3). Socioeconomic associations are detailed in table S5.
Multivariable logistic regression: adjusted odds ratios (95%CI) for cardiovascular risk factors (N=2800-2963)
| Covariate | Elevated BP | Obesity | Smoking | Physical inactivity | Non-optimal LDL-C | Elevated TG |
|---|---|---|---|---|---|---|
| Age (per y) | 1.05 (1.04-1.06)a | 1.00 (0.99-1.01) | 0.95 (0.93-0.96)a | 0.99 (0.98-1.00)b | 0.97 (0.96-0.98)a | 1.01 (1.00-1.02)b |
| Female sex | 0.61 (0.52-0.71)a | 0.73 (0.62-0.86)a | 0.87 (0.72-1.05) | 1.37 (1.17-1.60)a | 0.96 (0.83-1.12) | 1.34 (1.15-1.56)a |
| Area B (ref: Area A) | 1.28 (1.05-1.57)b | 1.24 (1.00-1.53) | 0.77 (0.60-0.98)b | 1.29 (1.05-1.58)b | 0.95 (0.78-1.16) | 1.75 (1.44-2.13)a |
| Area C | 1.27 (1.02-1.59)b | 1.23 (0.98-1.55) | 0.78 (0.59-1.02) | 1.26 (1.01-1.58)b | 0.86 (0.69-1.07) | 1.04 (0.83-1.29) |
| Area D | 1.21 (0.97-1.52) | 1.02 (0.81-1.30) | 0.77 (0.59-1.02) | 0.85 (0.68-1.07) | 1.24 (1.00-1.55) | 1.31 (1.06-1.63)b |
| Latin American origin (ref: Spain) | 0.76 (0.56-1.03) | 1.02 (0.75-1.40) | 0.21 (0.13-0.35)a | 1.45 (1.08-1.93)b | 1.03 (0.77-1.39) | 1.53 (1.15-2.04)c |
| Other origin | 1.09 (0.75-1.57) | 1.05 (0.72-1.54) | 0.84 (0.55-1.29) | 1.27 (0.89-1.82) | 1.15 (0.79-1.66) | 1.29 (0.91-1.84) |
| Low education (ref: high) | 1.45 (1.05-1.99)b | 2.08 (1.49-2.90)a | 1.25 (0.82-1.88) | 1.71 (1.24-2.36)c | 0.87 (0.63-1.20) | 1.09 (0.80-1.48) |
| Intermediate education | 1.39 (1.14-1.69)a | 1.64 (1.32-2.03)a | 1.36 (1.07-1.74)b | 1.49 (1.22-1.82)a | 0.90 (0.75-1.09) | 0.93 (0.77-1.12) |
| Income <1100 (ref:> 3900) | 1.30 (0.91-1.85) | 1.32 (0.90-1.92) | 3.25 (2.09-5.03)a | 1.26 (0.88-1.81) | 1.14 (0.80-1.63) | 1.20 (0.85-1.69) |
| Income 1100-1800 | 1.20 (0.90-1.60) | 1.17 (0.86-1.60) | 1.98 (1.37-2.86)a | 1.15 (0.86-1.54) | 0.97 (0.73-1.28) | 1.23 (0.94-1.62) |
| Income 1801-2700 | 1.16 (0.87-1.53) | 1.18 (0.88-1.60) | 1.78 (1.24-2.54)c | 1.29 (0.97-1.71) | 1.02 (0.78-1.34) | 1.17 (0.90-1.53) |
| Income 2701-3900 | 0.97 (0.73-1.30) | 0.92 (0.67-1.26) | 1.44 (0.99-2.09) | 1.19 (0.89-1.60) | 1.11 (0.84-1.46) | 1.08 (0.82-1.42) |
| Income trend (OR/cat)d | 0.93 (0.86-1.00) | 0.92 (0.85-0.99)b | 0.78 (0.72-0.86)a | 0.97 (0.90-1.05) | 1.00 (0.93-1.08) | 0.95 (0.88-1.02) |
BP, blood pressure; BMI, body mass index; LDL-C, low-density lipoprotein cholesterol; TG, triglycerides.
Smoking showed the steepest socioeconomic gradient. Participants in the lowest income category (< 1100 €/mo) had more than 3 times the odds of being active smokers compared with the highest (> 3900 €/mo): aOR, 3.25 (95%CI, 2.09-5.03; P <.0001). The intermediate income category (1100-1800 €/mo) also showed significantly elevated odds (aOR, 1.98; 95%CI, 1.37-2.86; P=.0003). The ordinal trend test confirmed a significant dose-response relationship (OR per income category increase, 0.784; 95%CI, 0.716-0.857; P <.0001). Female sex showed a nonsignificant trend toward lower odds of smoking (aOR, 0.87; 95%CI, 0.72-1.05); older age was significantly associated with lower odds (aOR, 0.95 per year; 95%CI, 0.93-0.96; P <.0001).
Hypertension (elevated blood pressure) showed a significant crude association with income (lowest vs highest: crude OR, 1.71; 95%CI, 1.25-2.35; P=.0008), which was attenuated after multivariable adjustment (aOR, 1.30; 95%CI, 0.91-1.85; P=.170), suggesting that education explains part of the crude income-hypertension relationship. Both education levels were independently associated with elevated blood pressure, as were older age and male sex (table 3). Area B and area C showed significantly higher odds of elevated blood pressure than area A (aORs, 1.27-1.28), while area D showed a nonsignificant trend (aOR, 1.21; 95%CI, 0.97-1.52).
Obesity showed the strongest association with educational level: both low and intermediate categories increased the odds, with a significant inverse income trend; female sex was protective (table 3).
Physical inactivity was independently associated with low education and intermediate education, and with female sex; no significant income trend was found after adjustment (table 3).
Nonoptimal LDL-C showed no significant association with income (trend OR, 1.00; 95%CI, 0.93-1.08; P_BH=.90) or educational level. The only significant covariate was age, with a slightly protective association (aOR, 0.97 per year; 95%CI, 0.96-0.98; P <.0001).
Elevated triglycerides were significantly associated with area B (aOR, 1.75; 95%CI, 1.44-2.13; P <.0001) and female sex (aOR, 1.34; 95%CI, 1.15-1.56; P <.0001). Income showed a nonsignificant inverse trend (OR per category, 0.949; 95%CI, 0.884-1.018; P=.147).
Prediabetes was significantly associated with area D (aOR, 1.69; 95%CI, 1.34-2.12; P <.0001) and age (aOR, 1.05 per year; 95%CI, 1.03-1.06; P <.0001). The lowest income category did not reach significance (aOR, 1.05; 95%CI, 0.72-1.52; P=.81). Income did not show a significant trend (OR per category, 1.01; 95%CI, 0.93-1.09; P=.86).
After BH correction of the income trend tests, the inverse gradient remained significant only for smoking. The triglyceride gradient, significant in the unadjusted model, was attenuated after adjustment for country of origin. Nonoptimal LDL-C (P_BH=.90) and risky alcohol intake (P_BH=.18) did not show significant income gradients.
Risky alcohol intake showed no significant income gradient (trend P=.09). The strongest covariate was sex, with women showing substantially lower odds (aOR, 0.28; 95%CI, 0.23-0.34; P <.0001). Age was positively associated (aOR, 1.03; 95%CI, 1.02-1.05; P <.0001), and area D showed lower odds relative to area A (aOR, 0.70; 95%CI, 0.53-0.92; P=.011). Socioeconomic associations for risky alcohol and prediabetes are presented in table S5.
The age×income interaction (table S6) was statistically significant only for active smoking (interaction OR, 1.020; 95%CI, 1.008-1.033; P=.0014; P _BH=.012). The seven remaining CVRF showed no significant interaction after multiple-testing correction (all P_BH ≥ .30). The inverse income gradient for smoking was steeper in participants aged <60 years (OR per income increment, 0.75; 95%CI, 0.66-0.84; n=1460) than in those aged ≥ 60 years (OR, 0.84; 95%CI, 0.73-0.96; n=1503).
Sensitivity analyses using multiple imputation (m=5) for missing income data, performed with chained equations and predictive mean matching, yielded results consistent with the complete-case analysis (table S7). For active smoking, the adjusted OR per income category increment was 0.78 (95%CI, 0.71-0.85) under MICE, matching the complete-case estimate (OR, 0.78; 95%CI, 0.72-0.86; P <.001 in both). Adjusted ORs for the remaining 7 outcomes differed by ≤0.02 between approaches, and conclusions on socioeconomic gradients were unchanged. The fraction of missing information across outcomes ranged from 0.03 to 0.25.
Implementation metrics and cost analysisThe participation rate was 41.8% (3545/8491), with clinical data completeness exceeding 99%. A total of 127 trained nurses across 42 primary care centers delivered the program over 3 months. The direct cost per participant was €11.75 (€0.50 per invitation letter plus €10.50 per capillary analysis disc plus €0.75 consumables).
For regional-scale implementation, the eligible population aged 40 to 75 years was estimated at 2 315 593 individuals (after excluding 47.2% with established cardiovascular disease, institutionalized individuals, those with recent vascular risk assessment, and immobile persons, through electronic health record cross-referencing). With invitations every 5 years by age cohort (analogous to cancer screening programs), the annual cohort amounted to 463 119 individuals. At 40% participation, the estimated annual direct material cost would be approximately €2.18 million.
DISCUSSIONThis study supports the operational feasibility of a nurse-led, single-visit cardiovascular screening program within Spanish primary care and reveals a high burden of modifiable risk factors and significant socioeconomic disparities, with smoking showing the steepest income gradient.
Feasibility and program performanceThe participation rate of 41.8% is comparable to the NHS Health Check (40%-50%)4,5 and is higher than some YOUNG50 pilots.7 Clinical data completeness exceeded 99%. The direct material cost of €11.75 per participant provides useful planning information, although this figure excludes personnel costs, which represent a substantial component of real-world implementation. Comparisons with other European programs that report total costs, including staffing, should therefore be made with caution.19 The high prevalence of previously undetected or uncontrolled risk factors supports systematic over opportunistic case-finding. Screening could leverage existing nursing infrastructure rather than requiring additional hiring. Notably, women comprised 56.7% of the analytical sample, a representation substantially higher than the less than 30% female participation typically observed in randomized controlled trials cited in current American and European cardiology guidelines.20 This balance strengthens the generalizability of our prevalence estimates and socioeconomic gradient findings for women in primary care settings (table S8, RE-AIM framework).
Cardiovascular risk factor prevalence in contextPrevalences (table 2) are broadly consistent with national age-standardized estimates (DARIOS, ENRICA),9,21 with elevated blood pressure and obesity slightly higher (reflecting the older age range and single-visit measurement)22–24 and smoking lower (reflecting age-related cessation).25 New-onset diabetes (2.0%) highlights the glycemic burden missed by opportunistic screening. The clinical relevance of detecting these factors in primary care is supported by evidence from the Spanish PESA cohort showing strong associations between obesity26 and prediabetes27 and subclinical atherosclerosis, even among individuals with otherwise low estimated cardiovascular risk.
SCORE2/SCORE2-OP classification identified 40.1% of participants at moderate or high 10-year cardiovascular risk, with marked sex and age differences (table S3). The oldest subgroup showed the highest proportion at moderate or high risk, underscoring the importance of including the oldest eligible cohort. These data suggest that universal screening would capture the substantial burden of individual risk factors present even among persons classified as being at low composite risk.
Socioeconomic gradientsThe multivariable analysis identified smoking as the CVRF with the strongest independent income gradient (aOR, 3.25 for the lowest vs highest income category). This finding is consistent with previous European data on persistent social gradients in smoking behavior,28,29 reinforcing the external validity of our findings; complementary targeted cessation interventions could be considered alongside universal screening.
Formal interaction analyses (table S6) indicated that the gradients observed for 7 of the 8 CVRFs operate consistently across the 50- to 77-year age range, supporting their interpretation as independent associations rather than age-driven artifacts. The steeper smoking gradient among participants younger than 60 years is compatible with a life-course pattern of widening tobacco-related inequalities across successive Spanish birth cohorts.
The attenuation of the income-hypertension association after adjustment for education suggests shared variance between these correlated indicators; education was independently associated with hypertension, obesity, and physical inactivity (table 3), consistent with knowledge-mediated pathways, although the cross-sectional design precludes causal ordering.30
The absence of a statistically significant LDL gradient after BH correction (P_BH=.90) warrants further investigation with prescription data in the expanded program; insufficient statistical power cannot be excluded as an alternative explanation. These associations should be interpreted with caution given the cross-sectional design, the 16% missing income data, and potential participation bias, which may affect the magnitude of the observed inequalities.
Significant geographic variation for several risk factors persisted after individual-level socioeconomic adjustment, suggesting that area-level factors may exert independent effects on cardiovascular risk, a hypothesis the expanded program will be better powered to investigate.31
From pilot to policyThe regional health authority used these pilot data to approve the expanded program in a Spanish autonomous community, with implementation beginning in 2026. This iterative process provides a model for other decentralized European health systems requiring region-specific evidence.32
LimitationsSeveral limitations should be considered. The cross-sectional design precludes causal inference. Blood pressure was measured twice during the same visit when the first reading was elevated; however, same-visit measurements may still overestimate the prevalence of hypertension compared with repeated assessments on separate occasions. The LDL-C threshold for participants without ACVD (≥ 116mg/dL, corresponding to the ESC-recommended LDL-C goal of <3.0 mmol/L for low-risk individuals) was applied as a single operational cutpoint and did not incorporate the full ESC risk-stratified targets (≥ 55, 70, and 100mg/dL for individuals at very-high, high, and moderate cardiovascular risk, respectively). Obesity was assessed by BMI only, without waist circumference measurement.23 Selection bias from the 41.8% participation rate and 16.0% missing income data may attenuate the magnitude of observed inequalities; the results derive from a single region in winter and may not be fully generalizable. Interobserver variability among the 127 participating nurses was not formally assessed. Costs excluded personnel, and follow-up data on cardiovascular events were unavailable. Point-of-care HbA1c measurements may also differ slightly from laboratory-based values.
The pilot protocol did not collect data on current pharmacological treatment, a methodological gap that we acknowledge limits the assessment of risk factor control and treatment effectiveness; the expanded program will address this through linkage to electronic prescription records.
Methodologically, odds ratios with prevalences exceeding 30% may overestimate association magnitudes; sensitivity analyses using modified Poisson regression with robust variance and cluster-robust standard errors yielded consistent direction and significance.33
CONCLUSIONSA nurse-led, single-visit cardiovascular screening program with point-of-care testing is operationally feasible in Spanish primary care, achieving a participation rate of 41.8% and clinical data completeness exceeding 99%. The study identified a high burden of modifiable risk factors and significant socioeconomic disparities. Smoking showed the steepest income-associated gradient among modifiable cardiovascular risk factors (aOR, 3.25 for the lowest income category), while educational level was independently associated with hypertension, obesity, and physical inactivity. The absence of a significant LDL-C gradient warrants further investigation with prescription data. This pilot led to the approval of the first systematic cardiovascular screening program in a Spanish autonomous community. Longitudinal studies are needed to determine the impact on cardiovascular events and the equity of benefit across socioeconomic groups.34
DATA AVAILABILITYThe deidentified data supporting this study are available from the corresponding author upon reasonable request.
FUNDINGThis work received unconditional support for research and dissemination activities from Fundación Occident, Fundación Interhospitalaria para la Investigación Cardiovascular, Amgen, and Lilly. The funders had no role in the study design, data collection, analysis or interpretation, or in the decision to submit the article for publication.
ETHICAL CONSIDERATIONSThis study was approved by the Clinical Research Ethics Committee of Hospital Clínico San Carlos, Madrid, Spain (code 22/237-E). All participants provided written informed consent. The study was conducted in accordance with the Declaration of Helsinki. SAGER guidelines: sex-disaggregated data are reported throughout (cardiovascular risk classification by sex, smoking prevalence by sex, multivariable models adjusted for sex). The study population comprised 56.7% women and 43.3% men. Sex differences in risk factor prevalence and SCORE2 classification are discussed.
STATEMENT ON THE USE OF ARTIFICIAL INTELLIGENCEDuring the preparation of this work, the authors used Claude (Anthropic) to assist with language editing and manuscript formatting. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the publication.
AUTHORS’ CONTRIBUTIONSC. Bengoa Terrero and J. Flores Soler: conceptualization, formal analysis, funding acquisition, investigation, methodology, project administration, resources, visualization, and writing of the original draft. J.E. Villares Rodríguez: conceptualization, supervision, and writing (review and editing). T. Blanco Maestro: data curation, investigation, and project administration. C. Vergara Uzcategui: data curation, investigation, project administration, and writing (review and editing). M. Bas Villalobos: conceptualization, funding acquisition, project administration, supervision, and writing (review and editing). M.R. Azcutia Gómez: conceptualization and supervision. J.I. Ten Morón: data curation, project administration, and software. C. Peinado Escobar: data curation, project administration, and software. C. Fernández Pérez: formal analysis, visualization, and writing (review and editing). E. Melero Cabadas: project administration. J. Pérez-Villacastín: conceptualization, funding acquisition, supervision, and writing (review and editing). A. Quintana Morgado: conceptualization and supervision. I. Vilacosta: conceptualization, funding acquisition, methodology, supervision, and writing of the original draft. All authors reviewed and approved the final manuscript.
CONFLICTS OF INTERESTNone declared.
- –
Cardiovascular diseases are the leading cause of mortality in Spain.
- –
European guidelines recommend systematic cardiovascular risk assessment every 5 years.
- –
Several European countries have population-based screening programs (NHS Health Check, CARDIO50), but no Spanish autonomous community has implemented a comparable program.
- –
This study demonstrates the operational feasibility of a nurse-led, single-visit cardiovascular screening program (41.8% participation,> 99% data completeness, EUR 11.75/participant) and quantifies socioeconomic disparities through multivariable regression, identifying smoking as the steepest income-related inequality (aOR, 3.25).
- –
This pilot study led to the approval of the first systematic cardiovascular screening program in a Spanish autonomous community (256 centers, approximately 463 000 individuals/y).
The authors thank all collaborating staff of PreveCardio for their essential contributions to data collection. We acknowledge the support received from the Primary Care Management of the Madrid Health Service under the direction of Sonia Martínez Machuca during the initial phase of the project. We also thank the organizations and funders for their commitment to primary prevention.
Supplementary data associated with this article can be found in the online version available at https://doi.org/10.1016/j.rec.2026.07.005.