
Tricuspid regurgitation (TR) is closely linked to heart failure (HF). However, the burden and predictors of HF hospitalization at diagnosis and during follow-up have not been fully characterized, particularly after accounting for the competing risk of death.
MethodsWe conducted a retrospective multicenter cohort study including 757 patients with significant TR. Prevalent HF was defined as HF hospitalization at the time of diagnosis. Among patients without prevalent HF, the cumulative incidence of first HF hospitalization was assessed using competing risk analysis, with all-cause mortality treated as a competing event. Multivariable models were used to identify independent predictors.
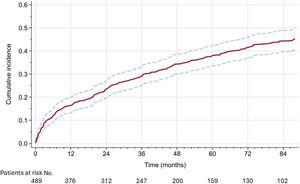
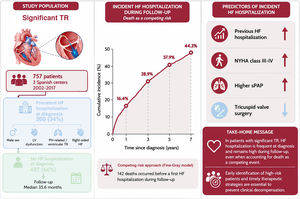
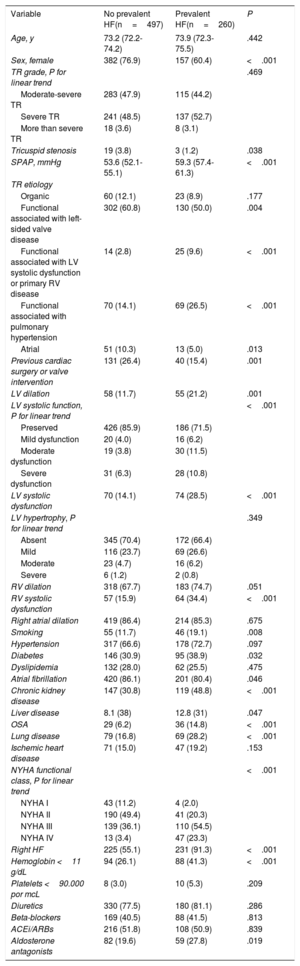
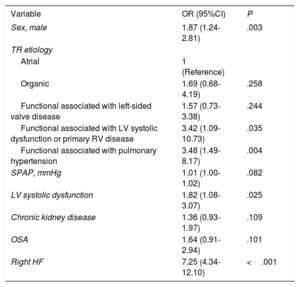
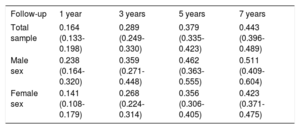
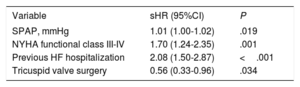
ResultsAt diagnosis, 260 patients (34.4%) were hospitalized for HF. Male sex, right-sided HF, left ventricular systolic dysfunction, and TR etiologies related to ventricular dysfunction or pulmonary hypertension were independently associated with prevalent HF. Among patients without prevalent HF (n=497), the cumulative incidence of HF hospitalization was 16.4% at 1 year and 44.3% at 7 years. Independent predictors of incident HF included prior HF hospitalization (sHR, 2.08; 95%CI, 1.50-2.87), NYHA functional class III-IV (sHR, 1.70; 95%CI, 1.24–2.35), and higher pulmonary artery systolic pressure (sHR, 1.01; 95%CI, 1.00-1.02). Tricuspid valve surgery was associated with a lower risk of HF hospitalization (sHR, 0.56; 95%CI, 0.33-0.96).
ConclusionsHF hospitalization is common in patients with significant TR, both at diagnosis and during follow-up. HF hospitalization at the time of diagnosis identifies an advanced clinical phenotype, while incident hospitalization remains frequent after accounting for the competing risk of death.
Keywords
Abbreviations
Identify yourself
Not yet a subscriber to the journal?
Purchase access to the article
By purchasing the article, the PDF of the same can be downloaded
Price: 19,34 €
Phone for incidents
Monday to Friday from 9am to 6pm (GMT+1) except for the months of July and August, which will be from 9am to 3pm