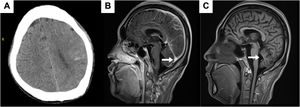

A 34-year-old man was admitted for seizures and loss of consciousness. He had a history of ophthalmic surgeries for vitreous opacities and cataracts. Brain computed tomography confirmed subarachnoid hemorrhages (figure 1A), and cerebrospinal fluid analysis revealed elevated protein levels (2.7g/L). Brain magnetic resonance imaging (MRI) showed diffuse leptomeningeal enhancement and mild cerebral atrophy (figure 1B,C, arrow). Informed consent was obtained for all diagnostic procedures.

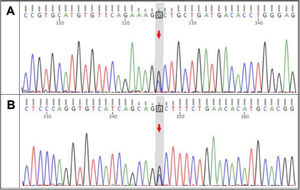
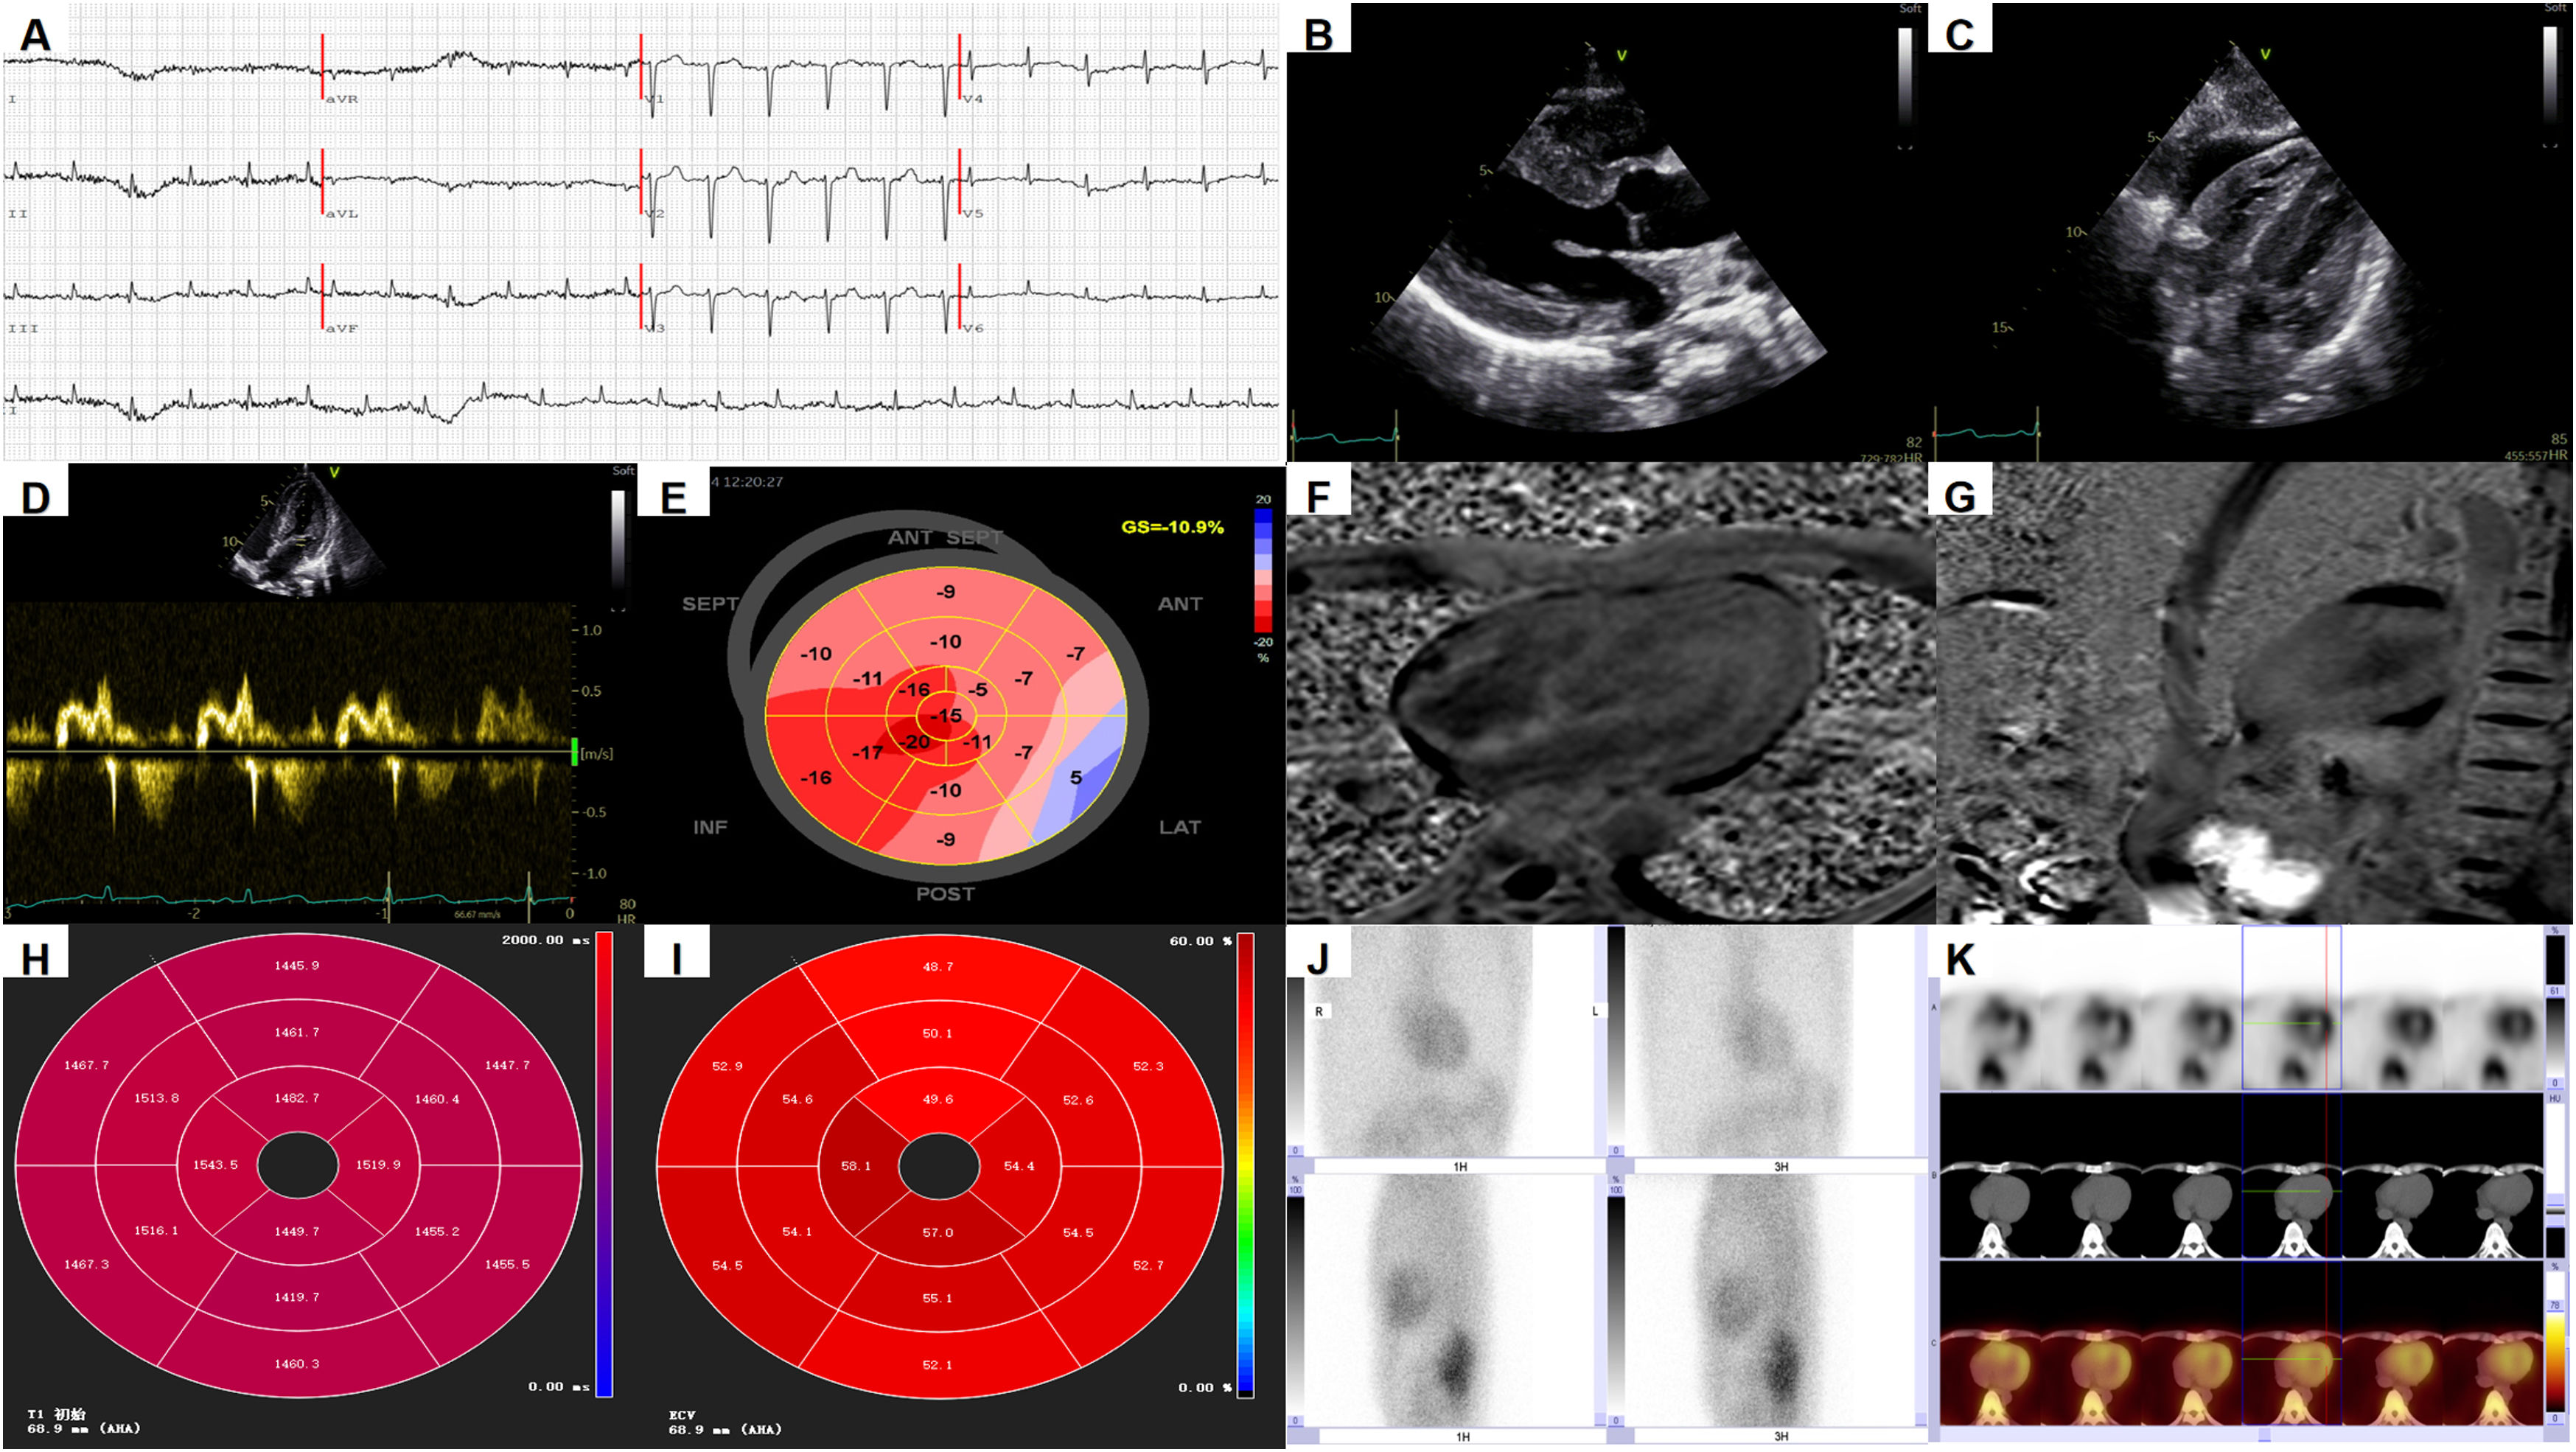
Electrocardiography revealed sinus tachycardia and low voltage in the limb leads (figure 2A). Laboratory examinations showed normal N-terminal pro-B-type natriuretic peptide and troponin I levels. Echocardiography demonstrated marked biventricular hypertrophy (interventricular septal thickness, 15mm), a left ventricular ejection fraction of 66%, abnormal global longitudinal strain (–10.9%), and an ejection fraction to global longitudinal strain ratio of 6.1 (figure 2B-E; videos S1-S3). Cardiac MRI demonstrated diffuse biventricular transmural late gadolinium enhancement, increased T1 signal (1465 ms), and elevated extracellular volume (53%) (figure 2F-I). Serum and urine immunofixation electrophoresis showed no monoclonal protein. 99mTc-pyrophosphate scintigraphy demonstrated grade 3 myocardial uptake, and single-photon emission tomography imaging indicated diffuse myocardial uptake (figure 2J, K). Finally, genetic testing revealed a c.166G>C (p.Ala56Pro) transthyretin (TTR) mutation, confirming oculoleptomeningeal amyloidosis (OLMA) with severe cardiac involvement (figure 3).


TTR is primarily produced by the liver, but also by the choroid plexuses and retinal pigment epithelium. In OLMA, pathogenic TTR disproportionately accumulates in these regions. Previous reports have primarily shown ophthalmic and neuropathic phenotypes at initial presentation in p.Ala56Pro carriers. Our case report expands the phenotypic spectrum, presenting cardiomyopathy in OLMA with severe infiltration but normal biomarkers, suggesting a distinct phenotype from classic TTR amyloidosis cardiomyopathy.
FUNDINGThis work was supported by the National Natural Science Foundation of China (grant numbers 82572250 and 82472007), the Natural Science Foundation of Liaoning Province (grant number 2024-MSLH-546), and the General Program of China Postdoctoral Science Foundation (grant number 2025M772283).
ETHICAL CONSIDERATIONSThe study was conducted in accordance with the principles of the Declaration of Helsinki. The authors confirm that informed consent was obtained for all tests and interventions and for the publication of the case. Possible sex and gender biases have been considered, in accordance with SAGER guidelines.
STATEMENT ON THE USE OF ARTIFICIAL INTELLIGENCEArtificial intelligence has not been used in the preparation of this manuscript.
AUTHORS’ CONTRIBUTIONSC.-W. Wang and Y.-H. Wang collected the data and wrote the clinical case and its discussion. C.-Y. Ma selected, provided, and prepared the images shown in the clinical case and supervised the manuscript drafting. Y.-H. Wang and C.-Y. Ma contributed equally to this work as co-corresponding authors. All authors approved the final version of the manuscript.
CONFLICTS OF INTERESTThe authors declare that they have no conflicts of interest related to the publication of this manuscript.
Supplementary data associated with this article can be found in the online version available at https://doi.org/10.1016/j.rec.2026.05.001.