
Incident heart failure (iHF) impacts the downstream cardiovascular disease continuum, particularly after acute coronary syndromes (ACS). The aim of this study was to assess iHF after ACS from a population-based perspective, identify its risk factors, and analyze the associated clinical and resource burden.
MethodsRetrospective, population-based study including all individuals covered by the Catalonian public health care system, who were discharged after an ACS between January 1, 2011 and December 31, 2021. Integrated health care databases from multiple sources were used.
ResultsAmong 83 357 patients without previous HF who were discharged after ACS, 23.3% developed iHF during follow-up. The main risk factors for developing iHF after ACS included age (sHR, per year 1.03; 95%CI, 1.03-1.04), very low income (sHR, 2.08; 95%CI, 1.56-2.78), and Killip class II-III at presentation (sHR, 2.16; 95%CI, 2.06-2.27). Compared with patients without iHF, those who developed iHF had markedly higher rates of all-cause mortality (3.44-fold), major adverse cardiac events (2.75-fold), and substantially greater health care expenditure, mainly driven by hospitalizations.
ConclusionsOne in 4 ACS survivors developed HF within 10 years, with major consequences for survival, morbidity, and health care costs. Socioeconomic status emerged as a determinant comparable to traditional clinical risk factors, suggesting the importance of targeted strategies to improve early identification and prevention of HF after ACS, particularly in socioeconomically vulnerable populations.
Registered at ClinicalTrials.gov (NCT06255418).
Keywords
Abbreviations
The concept of the cardiovascular (CV) disease continuum encompasses the wide spectrum of conditions that affect the CV system, beginning with risk factors (eg, dyslipidemia, hypertension) and progressing through coronary artery disease to heart failure (HF) and, ultimately, end-stage heart disease. Within the spectrum of coronary artery disease, acute coronary syndromes (ACS)—including ST-segment elevation myocardial infarction (STEMI), non–ST-segment elevation myocardial infarction (NSTEMI), and unstable angina (UA)—are among the most critical events driving progression along the CV continuum toward the development of HF.1
Current therapeutic strategies mainly focus on secondary prevention after the initial cardiovascular event.2 Although incident heart failure (iHF) has a major impact on the cardiovascular disease continuum, particularly after ACS,3 it has been neglected in postmyocardial infarction prevention studies, which have prioritized short-term mortality and recurrent coronary events.4–6 Addressing iHF after ACS is essential, given its association with disease progression,7 impaired quality of life,8 substantial economic burden,9 and its potential preventability (ie, the incidence and progression of HF can be mitigated),10ultimately improving outcomes and reducing healthcare costs
Despite the availability of real-world data on iHF after ACS, significant gaps in knowledge persist. All the previous studies addressing this issue have important limitations: the study populations were small, data were derived from the controlled settings of clinical trials (CARE and HORIZONS), the studies are not contemporary, none of these studies had a population-based perspective, and their temporal scope was limited.11–18 The lack of this information may explain why iHF has not been a primary focus of secondary prevention strategies after ACS.
Therefore, we designed a study to improve understanding of iHF after ACS, from a population-based perspective, in the mid- and long-term. Our main aims were to estimate the incidence rate of HF after ACS and to characterize patients with ACS at the population level. We also assessed risk factors for HF after ACS, the cumulative incidence and probability of major clinical outcomes in patients with and without iHF in the short- and long-term, and the impact of developing iHF after ACS on health care resource use and expenditure.
METHODSStudy context and data sourceThis study was conducted in Catalonia, an autonomous region in north-east Spain with 7.76 million inhabitants as of January 2022. Data were obtained from the Catalan Health Surveillance System (CHSS), a population-based registry managed by the Catalan Health Department.19,20 The CHSS compiles demographic, socioeconomic, diagnostic, and health care utilization data for all individuals covered by the public health care system. It integrates information from multiple sources, including the Minimum Dataset for Health care Units (hospitalizations, primary care, skilled nursing, outpatient specialist visits, and emergency care), pharmacy prescription records, and billing data. Until 2017, diagnoses were coded using ICD-9-CM, ICD-10-CM, or ICPC-2, depending on the care setting. From 2018 onwards, the ICD-10-CM was adopted in hospitals and primary care. All diagnoses were harmonized to ICD-10-CM, procedures were coded using ICD-9 until 2017 and ICD-10 thereafter. Medications were classified according to ATC codes, and vital status was obtained from the Spanish National Statistics Institute.
Study designIn this retrospective, population-based study, we analyzed data from the CHSS between January 2011 and December 2021, covering an 11-year period. The study was registered at ClinicalTrials.gov (NCT06255418) as BEAT-HF (Big data & real-world Evidence to assess the healthcare and health outcomes burden of Acute coronary syndromes complicaTed with Heart Failure). Ethics approval was obtained from the Clinical Research Ethics Committee of the Bellvitge Biomedical Research Institute, Spain, and the study complied with the Declaration of Helsinki. Owing to its retrospective design and use of pseudonymized data, informed consent was waived.
ParticipantsWe included data from all residents of Catalonia covered by the public health care system who were diagnosed with ACS during a hospitalization episode due to NSTEMI, STEMI, or UA and were discharged between January 1, 2011 and December 31, 2021 according to the prespecified diagnostic coding described in table S1. We excluded patients who had been diagnosed with HF in the years preceding the study period and those who died before discharge. iHF was defined using the following criteria: a) first hospitalization with a primary diagnosis of HF after the index ACS (table S2), or b) first HF diagnosis recorded in primary care after the index ACS plus concurrent prescription of loop diuretics to validate the diagnosis.
Objectives, outcomes, and measuresThe first coprimary objective was to describe the baseline characteristics of the surviving ACS population overall and according to the event type (STEMI, NSTEMI, UA) and other relevant subgroups of patients. The second coprimary objective was to investigate the real-world incidence of HF after ACS in all patients discharged after ACS. The secondary objectives of the study were: a) to ascertain the occurrence of important clinical outcomes after ACS, b) to describe the medical resource use and expenditure of the overall population of patients experiencing an ACS, and c) to analyze these data stratified according to iHF status.
We evaluated the following clinical outcomes: occurrence of all-cause mortality and need for CV procedures. Additional outcomes assessed comprised the occurrence of recurrent ACS, stroke, CV hospitalization, 4-point major adverse cardiac event (MACE) (all-cause mortality, recurrent ACS, new coronary revascularization, and stroke), and 5-point MACE (4-point MACE plus iHF).
We analyzed health care resource use (emergency, daycare, outpatient specialist, and primary care contacts, skilled nursing, and unplanned hospitalizations, including HF, CV, clinically related, and all-cause admissions) and associated costs (global, category-specific, and drug expenditure). Health care expenditure was calculated as previously described.21 Patients’ socioeconomic status was determined according to medicine copayment levels, as detailed elsewhere.19 Killip classification was used to assess ACS severity, ranging from no HF (Killip I) to cardiogenic shock (Killip IV). Clinical complexity was assessed using the Adjusted Morbidity Groups, which classify the population into 6 morbidity groups and have been validated in the Spanish and Catalan public health care systems.19–22
Statistical analysisBaseline characteristics are expressed as frequencies and percentages for categorical variables and the mean±standard deviation (SD) or 95% confidence interval (95%CI) for continuous variables, with group comparisons performed using the chi-square or Fisher exact tests and 1-way ANOVA.
Competing risk analyses were conducted using Fine and Gray proportional subhazards models with death and iHF as competing events, adjusting for relevant covariates (figure S1). Cumulative incidence functions, incidence rates, and time-to-first event analyses were conducted to evaluate fatal and nonfatal cardiovascular outcomes by HF status. Medical resource use and expenditure were compared among strata using the chi-square and nonparametric tests. Poisson models were used to assess health care utilization and Gaussian models (log-costs) for expenditure. Finally, mixed-effects generalized linear models with patients as random effects were used to assess the association between HF status and health care utilization and costs, adjusting for age, sex, income, clinical complexity, time since ACS, timing of health care delivery relative to ACS, and their interaction.
All statistical tests and 95%CI were constructed with a type I error alpha level of 5%, with no adjustments for multiplicity. P-values<.05 were considered statistically significant. All analyses were performed using R software (version 4.0.2; R Foundation for Statistical Computing, Vienna, Austria).
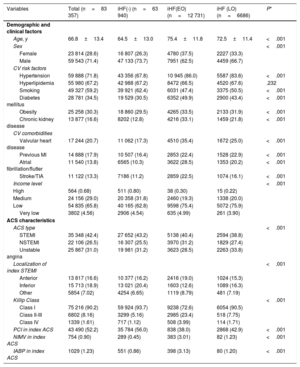
RESULTSBaseline characteristics and HF incidence ratePatient selection in this study is represented in figure S2. Between January 1, 2011 and December 31, 2021, 83 357 patients without previous HF were discharged after an ACS in Catalonia, Spain. The mean age of this overall population was 66.8±13.4 years and 71.4% (n=59 543) were men. During the study period, 19 417 (23.3%) individuals developed iHF [hereafter iHF(+) group]. Of them, 12 731 (15.3% of the entire cohort) developed iHF within the 2 years following the index event and were, therefore, considered early-onset (EO), while 6686 (8.0%) developed iHF 2 to 10 years after the index event (late onset, LO).
Table 1 compares iHF(-), iHF(EO), and iHF(LO) patients. Those with iHF were older, more often female, had more cardiovascular risk factors and prior disease, lower socioeconomic status, and less STEMI/NSTEMI. Killip II-III and anterior STEMI were more frequent in iHF(EO), while percutaneous coronary intervention (PCI) rates were lower in both iHF groups compared with the iHF(-) group (P <.001).
Baseline demographic, socioeconomic, and disease-related characteristics of patients included in the analysis, both overall and stratified according to incident heart failure status before 2 years (early-onset) and between 2 and 10 years (late-onset)
| Variables | Total (n=83 357) | iHF(-) (n=63 940) | iHF(EO) (n=12 731) | iHF (LO) (n=6686) | P* |
|---|---|---|---|---|---|
| Demographic and clinical factors | |||||
| Age, y | 66.8±13.4 | 64.5±13.0 | 75.4±11.8 | 72.5±11.4 | <.001 |
| Sex | <.001 | ||||
| Female | 23 814 (28.6) | 16 807 (26.3) | 4780 (37.5) | 2227 (33.3) | |
| Male | 59 543 (71.4) | 47 133 (73.7) | 7951 (62.5) | 4459 (66.7) | |
| CV risk factors | |||||
| Hypertension | 59 888 (71.8) | 43 356 (67.8) | 10 945 (86.0) | 5587 (83.6) | <.001 |
| Hyperlipidemia | 55 980 (67.2) | 42 988 (67.2) | 8472 (66.5) | 4520 (67.6) | .232 |
| Smoking | 49 327 (59.2) | 39 921 (62.4) | 6031 (47.4) | 3375 (50.5) | <.001 |
| Diabetes mellitus | 28 781 (34.5) | 19 529 (30.5) | 6352 (49.9) | 2900 (43.4) | <.001 |
| Obesity | 25 258 (30.3) | 18 860 (29.5) | 4265 (33.5) | 2133 (31.9) | <.001 |
| Chronic kidney disease | 13 877 (16.6) | 8202 (12.8) | 4216 (33.1) | 1459 (21.8) | <.001 |
| CV comorbidities | |||||
| Valvular heart disease | 17 244 (20.7) | 11 062 (17.3) | 4510 (35.4) | 1672 (25.0) | <.001 |
| Previous MI | 14 888 (17.9) | 10 507 (16.4) | 2853 (22.4) | 1528 (22.9) | <.001 |
| Atrial fibrillation/flutter | 11 540 (13.8) | 6565 (10.3) | 3622 (28.5) | 1353 (20.2) | <.001 |
| Stroke/TIA | 11 122 (13.3) | 7186 (11.2) | 2859 (22.5) | 1074 (16.1) | <.001 |
| Income level | <.001 | ||||
| High | 564 (0.68) | 511 (0.80) | 38 (0.30) | 15 (0.22) | |
| Medium | 24 156 (29.0) | 20 358 (31.8) | 2460 (19.3) | 1338 (20.0) | |
| Low | 54 835 (65.8) | 40 165 (62.8) | 9598 (75.4) | 5072 (75.9) | |
| Very low | 3802 (4.56) | 2906 (4.54) | 635 (4.99) | 261 (3.90) | |
| ACS characteristics | |||||
| ACS type | <.001 | ||||
| STEMI | 35 348 (42.4) | 27 652 (43.2) | 5138 (40.4) | 2594 (38.8) | |
| NSTEMI | 22 106 (26.5) | 16 307 (25.5) | 3970 (31.2) | 1829 (27.4) | |
| Unstable angina | 25 867 (31.0) | 19 981 (31.2) | 3623 (28.5) | 2263 (33.8) | |
| Localization of index STEMI | <.001 | ||||
| Anterior | 13 817 (16.6) | 10 377 (16.2) | 2416 (19.0) | 1024 (15.3) | |
| Inferior | 15 713 (18.9) | 13 021 (20.4) | 1603 (12.6) | 1089 (16.3) | |
| Other | 5854 (7.02) | 4254 (6.65) | 1119 (8.79) | 481 (7.19) | |
| Killip Class | <.001 | ||||
| Class I | 75 216 (90.2) | 59 924 (93.7) | 9238 (72.6) | 6054 (90.5) | |
| Class II-III | 6802 (8.16) | 3299 (5.16) | 2985 (23.4) | 518 (7.75) | |
| Class IV | 1339 (1.61) | 717 (1.12) | 508 (3.99) | 114 (1.71) | |
| PCI in index ACS | 43 490 (52.2) | 35 784 (56.0) | 838 (38.0) | 2868 (42.9) | <.001 |
| NIMV in index ACS | 754 (0.90) | 289 (0.45) | 383 (3.01) | 82 (1.23) | <.001 |
| IABP in index ACS | 1029 (1.23) | 551 (0.86) | 398 (3.13) | 80 (1.20) | <.001 |
ACS, acute coronary syndromes; CV, cardiovascular; EO, early-onset (≤2 years); HF, heart failure; IABP, intra-aortic balloon pump; iHF (-), no incident HF; iHF (+), incident HF; LO, late-onset HF (> 2 years); MI, myocardial infarction; NIMV, noninvasive mechanical ventilation; NSTEMI, non–ST-elevation myocardial infarction; PCI, percutaneous coronary intervention; STEMI, ST-elevation myocardial infarction; TIA, transient ischemic attack.
The data are expressed as No. (%) or mean±standard deviation.
Fine and Gray's model identified key risk factors for developing iHF post-ACS: increasing age (subhazard ratios [sHR], per year, 1.03; 95%CI, 1.03-1.04), low income (sHR, 1.92; 95%CI, 1.45-2.54), very low income (sHR, 2.08; 95%CI, 1.56-2.78), and Killip II-III class (sHR, 2.16; 95%CI, 2.06-2.27). PCI during ACS admission was associated with lower risk (sHR, 0.72; 95%CI, 0.70–0.75). Figure S1 shows additional predictors, including hypertension (sHR, 1.12; 95%CI, 1.07-1.17), obesity (sHR, 1.16; 95%CI, 1.13-1.20), atrial fibrillation/flutter (sHR, 1.44; 95%CI, 1.39-1.49), peripheral arterial disease (sHR, 1.19; 95%CI, 1.15-1.24), and chronic kidney disease (sHR, 1.19; 95%CI, 1.14-1.23).
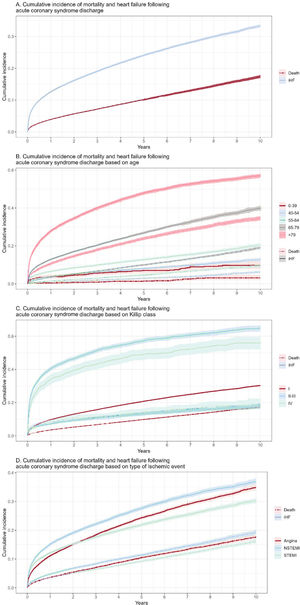
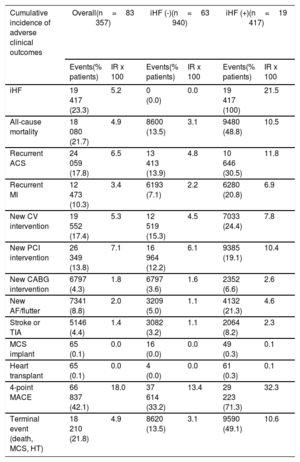
Cumulative incidence and probability of adverse clinical outcomes in patients after an ACS in the overall patient populationAs shown in table 2 and figure 1A, the incidence rate of HF after ACS was 5.2 new cases per 100 person-years of follow-up (table 2 and figure 1A). Overall, 23.3% developed iHF, 21.7% of the cohort died at the end of the study period, 17.8% developed recurrent ACS, 17.4% required a new CV intervention, and 42.1% had any of the 4-point MACE.
Cumulative incidence of adverse clinical outcomes both overall and stratified by incident heart failure
| Cumulative incidence of adverse clinical outcomes | Overall(n=83 357) | iHF (-)(n=63 940) | iHF (+)(n=19 417) | |||
|---|---|---|---|---|---|---|
| Events(% patients) | IR x 100 | Events(% patients) | IR x 100 | Events(% patients) | IR x 100 | |
| iHF | 19 417 (23.3) | 5.2 | 0 (0.0) | 0.0 | 19 417 (100) | 21.5 |
| All-cause mortality | 18 080 (21.7) | 4.9 | 8600 (13.5) | 3.1 | 9480 (48.8) | 10.5 |
| Recurrent ACS | 24 059 (17.8) | 6.5 | 13 413 (13.9) | 4.8 | 10 646 (30.5) | 11.8 |
| Recurrent MI | 12 473 (10.3) | 3.4 | 6193 (7.1) | 2.2 | 6280 (20.8) | 6.9 |
| New CV intervention | 19 552 (17.4) | 5.3 | 12 519 (15.3) | 4.5 | 7033 (24.4) | 7.8 |
| New PCI intervention | 26 349 (13.8) | 7.1 | 16 964 (12.2) | 6.1 | 9385 (19.1) | 10.4 |
| New CABG intervention | 6797 (4.3) | 1.8 | 6797 (3.6) | 1.6 | 2352 (6.6) | 2.6 |
| New AF/flutter | 7341 (8.8) | 2.0 | 3209 (5.0) | 1.1 | 4132 (21.3) | 4.6 |
| Stroke or TIA | 5146 (4.4) | 1.4 | 3082 (3.2) | 1.1 | 2064 (8.2) | 2.3 |
| MCS implant | 65 (0.1) | 0.0 | 16 (0.0) | 0.0 | 49 (0.3) | 0.1 |
| Heart transplant | 65 (0.1) | 0.0 | 4 (0.0) | 0.0 | 61 (0.3) | 0.1 |
| 4-point MACE | 66 837 (42.1) | 18.0 | 37 614 (33.2) | 13.4 | 29 223 (71.3) | 32.3 |
| Terminal event (death, MCS, HT) | 18 210 (21.8) | 4.9 | 8620 (13.5) | 3.1 | 9590 (49.1) | 10.6 |
ACS, acute coronary syndromes; AF, atrial fibrillation; CABG, coronary artery bypass grafting; CV, cardiovascular; HT, heart transplantation; iHF, Incident heart failure; iHF (-), did not develop incident heart failure; iHF (+), developed incident heart failure; IR x 100, incident rate per 100 person-years of follow-up; MACE, major adverse cardiovascular event (4-point, all-cause mortality, recurrent ACS, new coronary revascularization [either surgical or percutaneous], and stroke); MCS, mechanic circulatory support; MI, myocardial infarction; PCI, percutaneous coronary intervention; TIA, transient ischemic attack.

Cumulative incidence of heart failure and all-cause mortality following ACS hospitalization. A: in the whole cohort and according to B: age; C: Killip class; D: type of ACS. The shading indicates the 95% confidence interval. Competing risk between death and incident HF were considered in these analyses. ACS, acute coronary syndromes; iHF, incident heart failure; NSTEMI, non–ST-elevation myocardial infarction; STEMI, ST-segment elevation myocardial infarction.
Adverse clinical events increased markedly over time. The cumulative incidence of the 5-point MACE was 37% at 2 years, 51% at 5 years, and 66% at 10 years (figure S3). Older age and Killip class II-III were associated with higher rates of mortality and HR (figure 1). NSTEMI showed the highest incidence of death and HF, while UA surpassed STEMI in long-term HF risk. PCI rates were lower in patients with iHF.
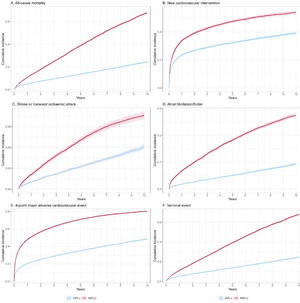
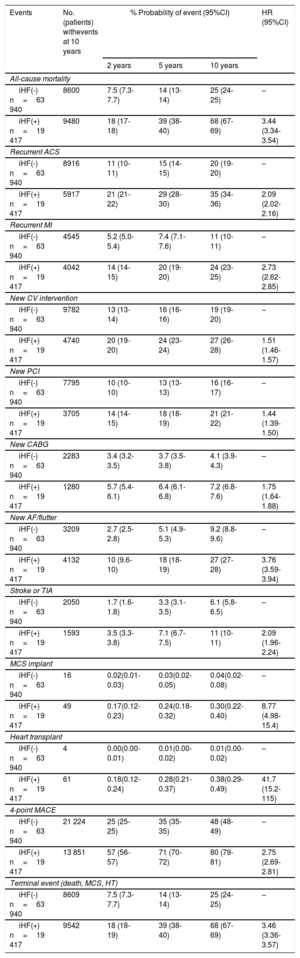
Cumulative incidence and probability of adverse clinical outcomes in patients after ACS among incident HF strataAs shown in table 2, table 3, and figure 2, iHF(+) patients experienced significantly more adverse outcomes than iHF(-) patients. Compared with iHF(-), risks were elevated for all-cause mortality (hazard ratio [HR], 3.44; 95%CI, 3.34-3.54), recurrent ACS (HR, 2.09; 95%CI, 2.02-2.16), myocardial infarction (HR, 2.73; 95%CI, 2.62-2.85), stroke/transient ischemic attack (HR, 2.09; 95%CI, 1.96-2.24), and 4-point MACE (HR, 2.75; 95%CI, 2.69–2.81).
Probability of experiencing fatal and nonfatal events cardiovascular events 2, 5 and 10 years after an ACS in the study population (n=83 357)
| Events | No. (patients) withevents at 10 years | % Probability of event (95%CI) | HR (95%CI) | ||
|---|---|---|---|---|---|
| 2 years | 5 years | 10 years | |||
| All-cause mortality | |||||
| iHF(-) n=63 940 | 8600 | 7.5 (7.3-7.7) | 14 (13-14) | 25 (24-25) | – |
| iHF(+) n=19 417 | 9480 | 18 (17-18) | 39 (38-40) | 68 (67-69) | 3.44 (3.34-3.54) |
| Recurrent ACS | |||||
| iHF(-) n=63 940 | 8916 | 11 (10-11) | 15 (14-15) | 20 (19-20) | – |
| iHF(+) n=19 417 | 5917 | 21 (21-22) | 29 (28-30) | 35 (34-36) | 2.09 (2.02-2.16) |
| Recurrent MI | |||||
| iHF(-) n=63 940 | 4545 | 5.2 (5.0-5.4) | 7.4 (7.1-7.6) | 11 (10-11) | – |
| iHF(+) n=19 417 | 4042 | 14 (14-15) | 20 (19-20) | 24 (23-25) | 2.73 (2.62-2.85) |
| New CV intervention | |||||
| iHF(-) n=63 940 | 9782 | 13 (13-14) | 16 (16-16) | 19 (19-20) | – |
| iHF(+) n=19 417 | 4740 | 20 (19-20) | 24 (23-24) | 27 (26-28) | 1.51 (1.46-1.57) |
| New PCI | |||||
| iHF(-) n=63 940 | 7795 | 10 (10-10) | 13 (13-13) | 16 (16-17) | – |
| iHF(+) n=19 417 | 3705 | 14 (14-15) | 18 (18-19) | 21 (21-22) | 1.44 (1.39-1.50) |
| New CABG | |||||
| iHF(-) n=63 940 | 2283 | 3.4 (3.2-3.5) | 3.7 (3.5-3.8) | 4.1 (3.9-4.3) | – |
| iHF(+) n=19 417 | 1280 | 5.7 (5.4-6.1) | 6.4 (6.1-6.8) | 7.2 (6.8-7.6) | 1.75 (1.64-1.88) |
| New AF/flutter | |||||
| iHF(-) n=63 940 | 3209 | 2.7 (2.5-2.8) | 5.1 (4.9-5.3) | 9.2 (8.8-9.6) | – |
| iHF(+) n=19 417 | 4132 | 10 (9.6-10) | 18 (18-19) | 27 (27-28) | 3.76 (3.59-3.94) |
| Stroke or TIA | |||||
| iHF(-) n=63 940 | 2050 | 1.7 (1.6-1.8) | 3.3 (3.1-3.5) | 6.1 (5.8-6.5) | – |
| iHF(+) n=19 417 | 1593 | 3.5 (3.3-3.8) | 7.1 (6.7-7.5) | 11 (10-11) | 2.09 (1.96-2.24) |
| MCS implant | |||||
| iHF(-) n=63 940 | 16 | 0.02(0.01-0.03) | 0.03(0.02-0.05) | 0.04(0.02-0.08) | – |
| iHF(+) n=19 417 | 49 | 0.17(0.12-0.23) | 0.24(0.18-0.32) | 0.30(0.22-0.40) | 8.77 (4.98-15.4) |
| Heart transplant | |||||
| iHF(-) n=63 940 | 4 | 0.00(0.00-0.01) | 0.01(0.00-0.02) | 0.01(0.00-0.02) | – |
| iHF(+) n=19 417 | 61 | 0.18(0.12-0.24) | 0.28(0.21-0.37) | 0.38(0.29-0.49) | 41.7 (15.2-115) |
| 4-point MACE | |||||
| iHF(-) n=63 940 | 21 224 | 25 (25-25) | 35 (35-35) | 48 (48-49) | – |
| iHF(+) n=19 417 | 13 851 | 57 (56-57) | 71 (70-72) | 80 (79-81) | 2.75 (2.69-2.81) |
| Terminal event (death, MCS, HT) | |||||
| iHF(-) n=63 940 | 8609 | 7.5 (7.3-7.7) | 14 (13-14) | 25 (24-25) | – |
| iHF(+) n=19 417 | 9542 | 18 (18-19) | 39 (38-40) | 68 (67-69) | 3.46 (3.36-3.57) |
95%CI, 95% confidence interval; ACS, acute coronary syndromes; AF, atrial fibrillation; CABG, coronary artery bypass grafting; CV, cardiovascular; HT, heart transplantation; HR, hazard ratio; iHF, incident heart failure; iHF (-), did not develop incident heart failure; iHF (+), developed incident heart failure; IR, incident rate; MACE, major adverse cardiovascular event (4-point, all-cause mortality, recurrent ACS, new coronary revascularization [either surgical or percutaneous], and stroke); MCS, mechanic circulatory support; MI, myocardial infarction; PCI, percutaneous coronary intervention; TIA, transient ischemic attack.

Cumulative incidence curves in patients with and without incident heart failure of A: all-cause mortality; B: new cardiovascular intervention; C: stroke or transient ischemic attack; D: new atrial fibrillation/flutter; E: 4-point major adverse cardiac event (all-cause mortality, recurrent ACS, new coronary revascularization [either surgical or percutaneous], and stroke), and F: terminal event (death, mechanic circulatory support, or heart transplantation). iHF (-), no incident heart failure; iHF (+), incident heart failure.
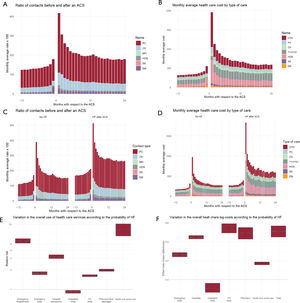
Health care contacts and costs increased slightly before ACS and peaked sharply during hospitalization, then declined but remained above baseline (figure 3A-3B). Mean total costs were more than twice as high in the first year (€6016±€8778) and 1.5 times higher in the second year (€4076±€7259) compared with the year before ACS (€2628±€5151), mainly driven by hospitalizations and pharmacy use. Hospital admissions were consistently higher in iHF(+) patients from 1 year before to 2 years after ACS (P <.001). Hospitalizations and pharmacy costs were the main cost drivers in both groups. Further information about trends in health care contacts and expenditure are summarized in figure 3C-D.

Ratio of contacts with the health care system and mean monthly expenditure before and after an ACS in the total population (A and B), and according to iHF status (C and D). Relative risk of medical resource use (E) and expenditure (F) before and after ACS and according to iHF status across different categories of health care services. ACS, acute coronary syndromes; AP, primary care; EM, emergency medicine visits; EXT, outpatient visits; PHARM, pharmacy; HF, heart failure; HOS, hospitalizations; iHF, incident heart failure; MH, mental health visits; OTH, outpatient hospitalizations; OV, outpatient visits; PC, primary care visits; SS, social services; URG, emergency visits.
As shown in figure 3E, mixed-effects adjusted models identified iHF(+) as an independent predictor of increased health care use compared with iHF(-), including higher monthly rates of primary care visits (incidence rate ratio [IRR], 1.63; 95%CI, 1.57-1.69), total hospital admissions (IRR, 3.18; 95%CI, 2.98-3.40), unplanned admissions (IRR, 5.56; 95%CI, 5.13-6.03), emergency visits (IRR, 1.77; 95%CI, 1.67-1.87), drug prescriptions (IRR, 1.97; 95%CI, 1.90-2.05), and social/health care services (IRR, 8.19; 95%CI, 6.61-10.20). Additionally, iHF(+) was associated with significantly higher overall health care expenditure (β, 0.73; 95%CI, 0.72-0.75; P <.001) (figure 3F).
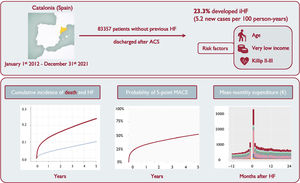
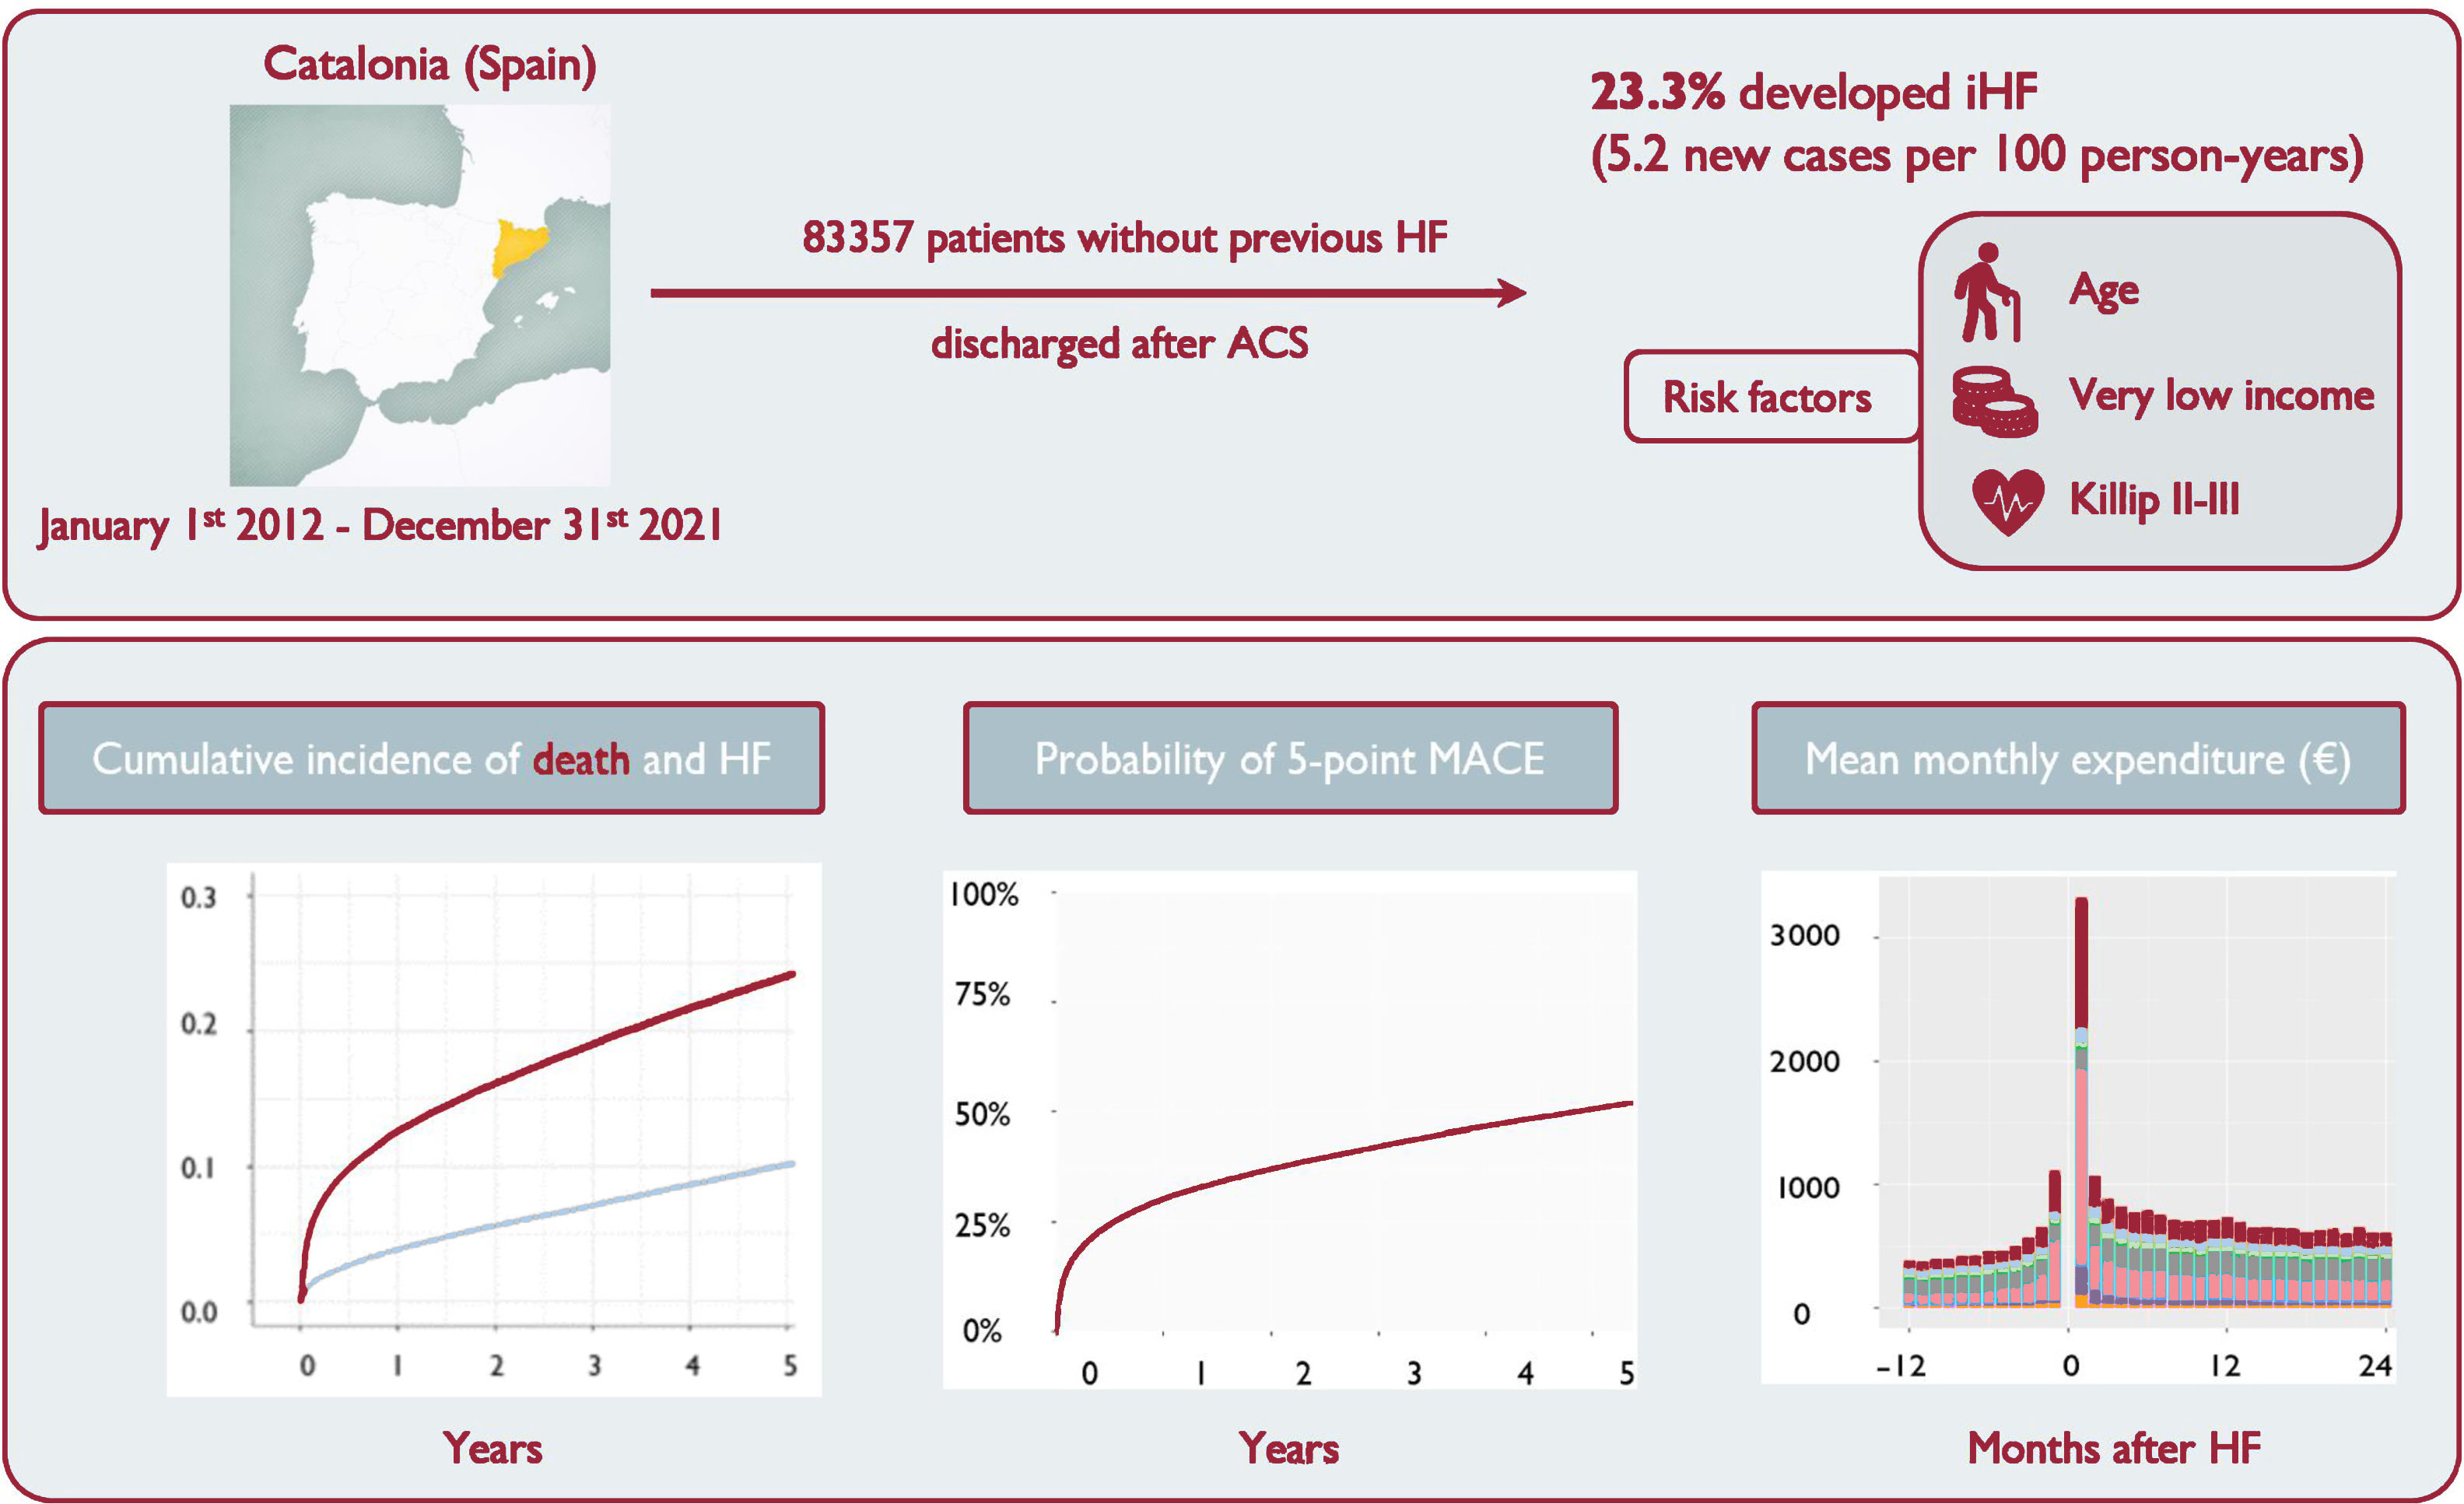
DISCUSSIONIn this population-based study, nearly 25% of patients with ACS developed HF within 10 years. Among those with iHF, 28% were diagnosed exclusively in hospital, 51% in both hospital and primary care settings, and 21% exclusively in primary care. iHF(+) patients were older, more often women, and had lower income. Killip class II-III and low and very-low income were the strongest predictors. iHF(+) was associated with higher mortality, a greater incidence of MACE, increased health care costs, and more terminal events, including heart transplantation. These findings are summarized in figure 4.

This study represents the largest population-based and longitudinal analysis of iHF following ACS hospitalization published to date. Previous evidence comes from smaller, pre-2011 clinical trials such as CARE (n=3860)23 and HORIZONS-AMI (b=3343).24 A population-based cohort study from Minnesota, also conducted before 2011, included fewer than 2000 individuals and had limited generalizability.25 A more recent registry of 337 274 myocardial infarction patients treated with PCI reported an iHF incidence of 18.8% within 5 years; however,> 90% underwent revascularization and patients with UA were excluded.26
A recently published study analyzed outcomes in more than 6800 myocardial infarction patients discharged from a US hospital network, reporting that nearly 1 in 4 developed iHF within 3 months, regardless of ejection fraction.18 While informative, this study had limitations: it was not population-based, potentially overestimating iHF incidence; follow-up was limited to 6 years; and no detailed data were provided on health care resource use or costs.
In contrast with previously mentioned studies, our work is, to the best of our knowledge, the first to provide population-based data on iHF after ACS within an entire health care system. By capturing all cases in Catalonia over a 10-year period and including the full spectrum of ACS (STEMI, NSTEMI, and UA), it offers a comprehensive and representative perspective that overcomes the selection biases inherent to hospital-based cohorts. Importantly, beyond long-term clinical outcomes, we also provide detailed information on health care resource utilization and associated costs. Notably, the incidence of postmyocardial infarction HF observed in our population-based analysis was lower than that reported in the US cohort, a difference likely attributable to patient selection, as our study captures the general population rather than a restricted hospital series.
In our population, the proportion of revascularization was around 50% at the index admission for ACS. This proportion differed from that in the previous study, where ≥ 90% underwent revascularization.18,26 This difference may be explained by the inclusion of only acute myocardial infarction patients in that study,26 whereas ∼30% of our cohort had UA, and by population selection bias. In our STEMI subgroup, 77% underwent PCI, consistent with previous findings.27 Our data reflect the entire population, including hospitals without 24/7 catheterization labs and the early phase of the infarction code program in Catalonia .28 Although evidence on revascularization in HF is limited, studies in ACS suggest that PCI, especially complete revascularization, is associated with reduced HF risk.14 We lacked data on whether PCI targeted only the culprit lesion or multiple vessels, but PCI was independently associated with a lower iHF incidence. The study period coincided with the implementation of infarction code in Catalonia, ensuring 24/7 access to primary PCI for STEMI patients throughout Catalonia, providing equitable emergency cardiac care in both urban and rural settings.28
Consistent with HORIZONS-AMI,24 our study found that advanced Killip class and anterior ACS location predicted iHF within 2 years. This risk persisted up to 10 years, with Killip ≥ II and age as the strongest predictors.23 Unlike previous studies, we identified very low socioeconomic status as a long-term predictor of iHF after ACS (sHR, 2.09; 95%CI, 1.57-2.78), with prognostic power comparable to Killip II/III class (sHR, 2.17; 95%CI, 2.07-2.27). The association between low socioeconomic status and iHF has not been well described in the literature; however, our group has previously linked low income to increased cardiovascular events in our setting.19
While the iHF(+) group had higher incidences of all types of analyzed adverse events, the largest difference between the 2 groups was found in all-cause mortality. The iHF(+) group showed higher rates of all adverse events, with the greatest difference in all-cause mortality, consistent with previous studies,23–26 although none matched our long-term scope. Higher health care expenditure before ACS suggests a worse baseline in iHF(+) patients, in agreement with evidence that comorbidities drive HF costs.9 Hospitalizations were the main cost driver, confirming findings from the single study focused on postmyocardial infarction HF economic burden.29 Advances in ACS care have improved survival but have also increased comorbidity burden, contributing to readmissions and rising costs. Given the epidemic trajectory of HF, its economic impact will likely grow, requiring proactive planning and resource allocation. Our findings highlight the need for validated risk scores incorporating clinical and socioeconomic factors to improve early detection and personalized care. The high burden of events and costs, especially due to HF—the final stage of the cardiovascular continuum—calls for new therapies to slow disease progression.30 Addressing post-ACS resource use and costs also demands integrated care strategies, equitable access, and coordinated hospital-primary care efforts. These findings might be generalizable to populations with comparable clinical profiles and health care systems.
Strengths and limitationsThe main strengths of this study include its large cohort size (∼8 million people), long follow-up, and high-quality data from a national registry. Importantly, it is the first to analyze health care resource use and expenditure in patients with ACS and iHF.
However, several limitations must be acknowledged. First, the population-based design relied on administrative diagnostic codes, which may not fully capture HF complexity. Indeed, iHF diagnoses included both hospitalized patients and those diagnosed in primary care without hospitalization, who may differ clinically; nevertheless, this approach reflects the full real-world spectrum of HF. We lacked detailed clinical data, such as ejection fraction, natriuretic peptides, and functional class, which limited phenotyping. In addition, the diagnosis of iHF was based on criteria widely used in previous studies, combining hospitalization with a primary diagnosis of HF and primary care records validated by loop diuretic prescription. Although this approach reflects real-world practice in integrated health care systems, we acknowledge that it may introduce heterogeneity in event definition.
Second, although Catalonia's universal health care system covers> 98% of cardiac care, data from private centers or outside the region were not included. Third, socioeconomic status was assessed only by income at the index event, without accounting for education, occupation, or changes over time. Fourth, while prescription data were available, medication adherence and lifestyle changes could not be evaluated. We also lacked information on complete vs incomplete revascularization during ACS. Fifth, changes in ACS management and coding practices over the decade may have influenced results, though sensitivity analyses showed consistency. Sixth, we found women had a higher incidence of iHF; however, these results may have been influenced by differences in ACS management among centers. Finally, while our findings are likely generalizable to other universal health care systems, they may not apply to settings with different structures or financial barriers to care.
CONCLUSIONSThis nationwide, real-world study shows that nearly 1 in 4 ACS survivors developed HF in the long term. The strongest predictors of iHF were older age, low income, and Killip II-III. The iHF(+) group had a significantly higher burden of adverse events and health care costs, mainly due to readmissions. Preventive strategies and risk scores, including socioeconomic factors, are needed to improve prognosis and reduce spending. The high rate of HF, the final stage of the cardiovascular continuum, highlights the urgent need for new therapies to slow or reverse disease progression.30 These findings support health policy action and may be generalizable to other universal health care systems.
FUNDINGThis project was financially supported by an unrestricted grant from AstraZeneca and by the Ministry of Health of Catalonia (Departament de Salut de la Generalitat de Catalunya) through Health Research and Innovation Strategic Plan PERIS 2023 (“Pla Estratègic de Recerca i Innovació en Salut 2023”) grant number SLT028/23/000018.
ETHICAL CONSIDERATIONSEthical approval was obtained from the Clinical Research Ethics Committee of the Bellvitge Biomedical Research Institute, Spain, and the study complied with the Declaration of Helsinki. Owing to its retrospective design and use of pseudonymized data, informed consent was waived. Reporting followed STROBE guidelines and SAGER guidelines with respect to possible sex/gender bias.
STATEMENT ON THE USE OF ARTIFICIAL INTELLIGENCEDuring the preparation of this work the authors used Chat-GPT to improve language and readability. After using this tool, the authors reviewed and edited the content as needed and takes full responsibility for the content of the publication.
AUTHORS’ CONTRIBUTIONSWe hereby confirm that all materials, data, and results presented in this manuscript are original to the authors. The work has not been published previously, in whole or in part, and is not under consideration for publication elsewhere. All authors have read and approved the final version of the manuscript and consent to its submission for publication.
CONFLICTS OF INTERESTJ. Comín Colet declares receiving unrestricted research grants, honoraria for speaking engagements, and consultancy fees from the study sponsor, AstraZeneca. The remaining authors declare no conflicts of interest related to this manuscript.
- –
ACS significantly increases the risk of developing HF over time. Until now, no population-based study had accurately quantified the long-term clinical consequences of progression along the cardiovascular continuum after ACS, or the substantial burden of this condition on health care systems.
- –
This large-scale, population-based study quantified the 10-year incidence of HF after ACS. This is the first study demonstrating that socioeconomic status is a major independent determinant, comparable to traditional clinical risk factors, and highlights the substantial clinical and economic burden. These findings highlight the urgent need to develop and implement integrated strategies for the prevention, early detection, and management of HF after ACS.
The authors would like to thank Matías Rey-Carrizo, PhD, at BCN Medical Writing for his medical writing support. We also thank the CERCA Programme/Generalitat de Catalunya for institutional support.
Supplementary data associated with this article can be found in the online version, available at https://doi.org/10.1016/j.rec.2026.02.003.