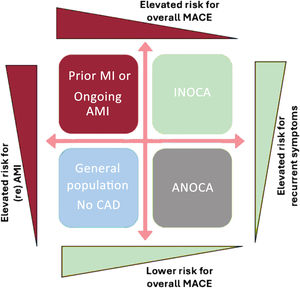


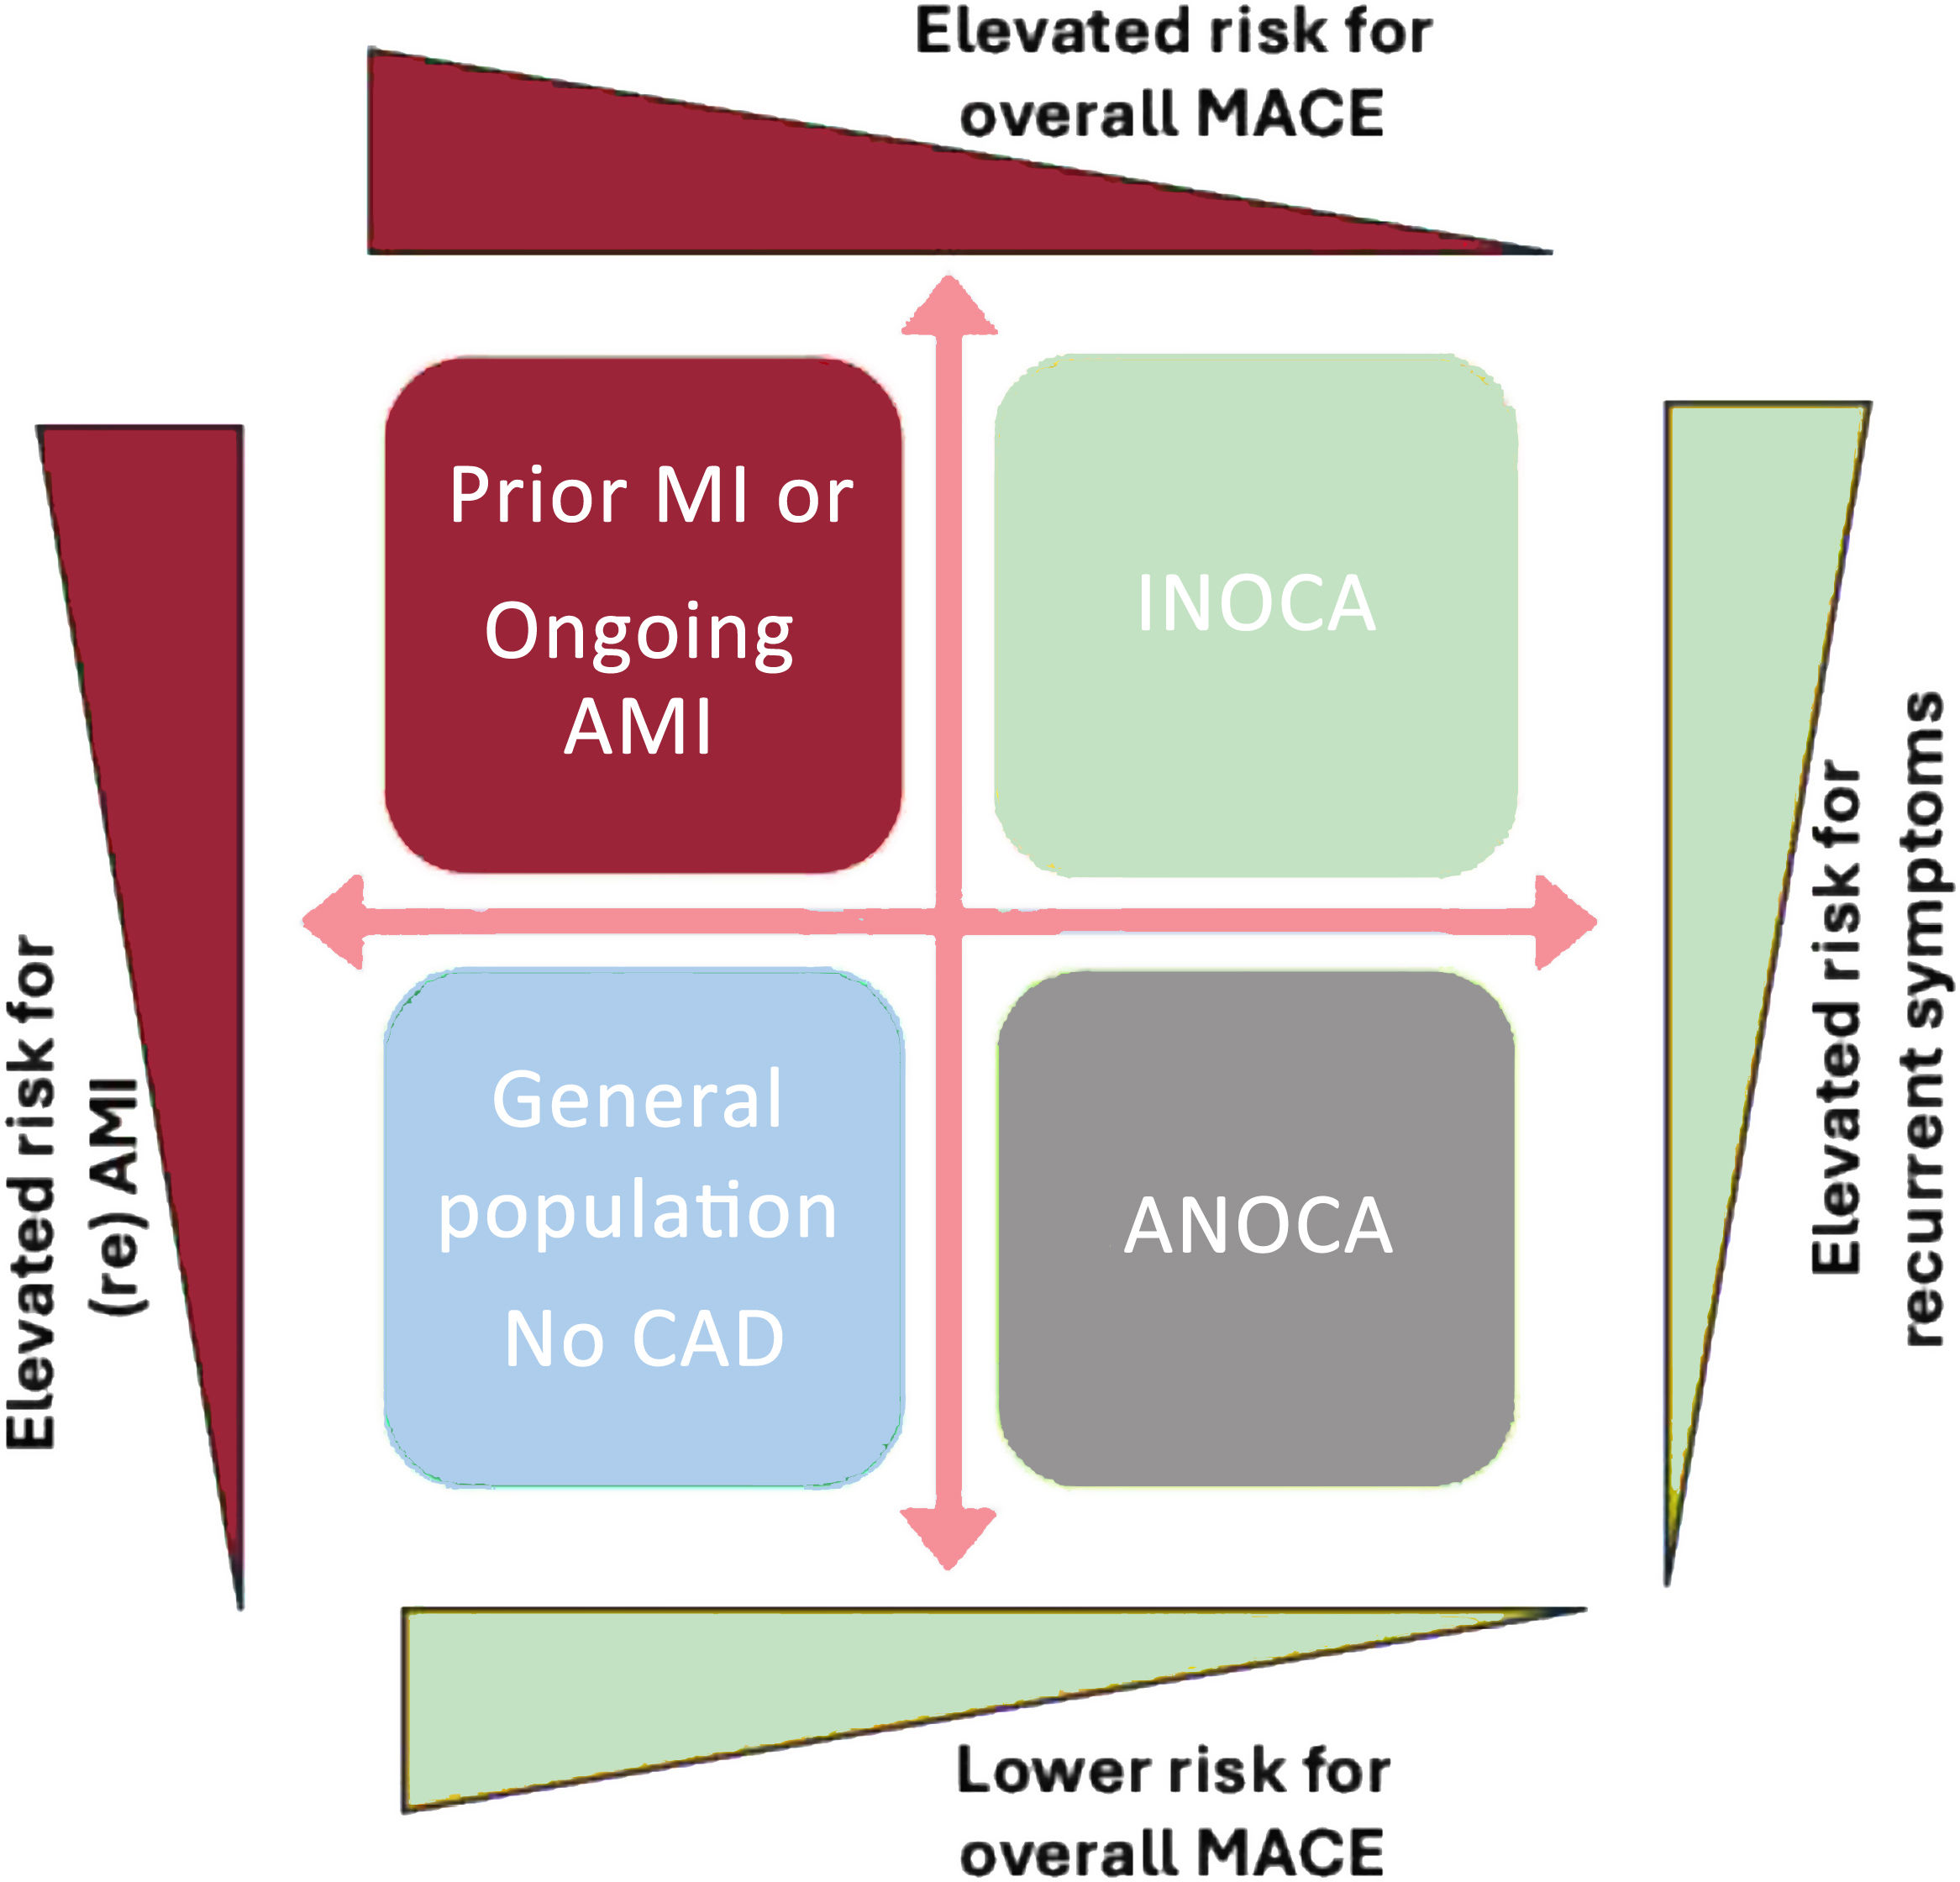
Ischemia and angina with nonobstructive coronary arteries (INOCA/ANOCA) have emerged as 2 of the most challenging and misunderstood entities in contemporary cardiovascular medicine.1 Are these entities merely “snapshots” of the natural history of coronary artery disease (CAD), rather than distinct syndromes requiring special considerations? Notably, patients with ANOCA appear to have a similar risk of myocardial infarction and lower mortality than the general population.2 This raises the question of whether these conditions may in some way precondition the heart, such that extensive acute myocardial infarction either does not occur or, when it does, is of lower severity. Furthermore, the identification of nonobstructive CAD, with or without any form of microvascular dysfunction (MVD), may place patients under closer clinical scrutiny, leading to intensified medical therapy and closer follow up, which could in turn reduce risk. In figure 1, we summarize the risk profile of patients with known CAD by their disease stage. Accordingly, patients with INOCA/ANOCA, particularly those with INOCA, may have an increased risk of recurrent symptoms but a lower risk of major adverse cardiac events.

Stages of coronary artery disease (CAD) according to clinical presentation and associated prognosis. Top left: patients with a prior myocardial infarction (MI) or an ongoing acute myocardial infarction (AMI) have the highest likelihood of recurrent MI, reflecting the principle that “an MI begets an MI,” as well as recurrent symptoms due to residual disease or failure of local therapy; top right: patients with ischemia with nonobstructive coronary arteries (INOCA) may develop MI, but their overall risk is low, while recurrent symptoms are frequent. Bottom panels: these depict the lowest-risk stages, in which the general population has a slightly higher likelihood of AMI and cardiac death than patients with angina with nonobstructive coronary arteries (ANOCA), possibly due to a prolonged preconditioning period or the effects of cardiovascular treatment in ANOCA patients. ANOCA, angina with nonobstructive coronary arteries; INOCA, ischemia with nonobstructive coronary arteries; MACE, major adverse cardiac events.
In 2020, a pivotal European Association of Percutaneous Cardiovascular Interventions (EAPCI) consensus document on INOCA paved the way for the interventional cardiology community by providing guidance on both the diagnosis and treatment of INOCA in clinical practice.3 In a recent article published in Revista Española de Cardiología, Rumiz et al.4 present one of the first and most detailed real-world evaluations to date of the INOCA endotypes proposed by the EAPCI consensus, offering valuable insights into the applicability of the standardized diagnostic algorithm and its clinical meaning. The study by Rumiz et al. describes a multicenter cohort of 308 patients undergoing comprehensive coronary function testing (CFT) in high-volume tertiary centers in Spain.4 The population exhibited typical INOCA demographics: predominantly older adults, with a high burden of cardiovascular risk factors, more than half experiencing exertional angina, and, notably, more than 20% having prior CAD, and 18.5% having previous percutaneous coronary interventions. CFT allowed classification into 4 primary endotypes: normal coronary function (24.3%), MVD(45.8%), epicardial spasm (21.4%), and mixed spasm (8.4%). Although baseline characteristics were broadly similar among groups, MVD and mixed spasm were more prevalent among women and older patients. Importantly, CFT proved safe, with only 1 major complication (0.3%) reported in the entire cohort. During a median follow-up of 1.8 years, 15.7% of patients experienced clinical events, predominantly recurrent chest pain requiring emergency evaluation.
Since emergency department visits constitute the most common “event,” and because not every visit should be adjudicated as related to ANOCA, we propose in figure 2 a definition for use in future INOCA/ANOCA studies.

Definition of emergency department visits. The bibliographical reference mentioned in this figure corresponds to Gutali et al.5.
The study by Rumiz et al.4 reported that event rates varied substantially by endotype: patients with CMD and mixed spasm demonstrated the highest incidence of recurrent symptoms, whereas those with normal CFT or isolated epicardial spasm fared considerably better. After multivariable adjustment, CMD, particularly the functional CMD subendotype, emerged as the only endotype independently associated with adverse outcomes, conferring a more than 6-fold increased risk compared with normal CFT. Taken together, these findings highlight the heterogeneity of INOCA and identify functional CMD as a distinct high-risk phenotype that warrants focused diagnostic attention and targeted therapeutic strategies.
Rumiz et al. should be congratulated for providing us with this detailed analysis of INOCA. Taken together, these findings highlight that INOCA, as currently diagnosed using CFT, represents a group of mechanistically distinct vascular disorders (all part of the natural history of CAD) with meaningful prognostic divergence reflecting their presence at different stages of the disease. Nevertheless, several limitations should be considered when interpreting these findings. First, the observational and nonrandomized design introduces the possibility of residual confounding and selection bias, particularly given that the decision to perform CFT was not systematically applied to all patients with suspected INOCA. Second, the exclusive use of bolus thermodilution to assess CFR and the index of microcirculatory resistance (IMR) may limit measurement reproducibility.6 Third, the inclusion of approximately 20% of patients with prior percutaneous coronary intervention may confound both physiological assessment and prognosis, as abnormalities in CFR or IMR, as well as subsequent outcomes, may reflect prior myocardial injury rather than true INOCA physiology. Fourth, the absence of longitudinal symptom and quality-of-life assessments limits the ability to relate clinical events to patient-reported outcomes. Fifth, although clinically informative, the follow-up period remains relatively short for a condition characterized by chronic morbidity, and longer observation may further clarify endotype-specific risk trajectories. Sixth, medical therapy following CFT was not standardized, limiting clinical reproducibility. Finally, the proportion of eligible patients who did not undergo CFT was not reported, raising the possibility of additional bias and limiting the representativeness of the cohort.
This work adds to the on-growing body of evidence strongly suggesting that physiologic endotyping must become part of routine coronary assessment in patients with angina and nonobstructive coronary arteries. Without it, clinicians are left to navigate INOCA with the blunt tools of probability and empiricism, risking both therapeutic inertia and inappropriate reassurance. Moreover, the prognostic implications reported here are noteworthy for several reasons. First, functional MVD demonstrated the highest incidence of recurrent events. Second, isolated high IMR was not associated with increased risk, highlighting that impaired CFR, rather than IMR alone, carries greater prognostic significance. This distinction is highly consistent with the ILIAS registry that show how CFR, by integrating multiple mechanistic pathways, remains the strongest physiologic predictor of clinical outcomes in INOCA.7 Third, the persistent vulnerability of functional MVD despite stratified medical therapy underscores an unmet therapeutic need. Unlike epicardial spasm—where near-universal use of calcium channel blockers translated into favorable outcomes—no existing therapy reliably improves CFR or reverses functional MVD.1 This gap between diagnostic precision and therapeutic capacity is now the central challenge in INOCA care.
Ultimately, the present study4 demonstrates that CFT-guided endotyping is feasible, safe, and clinically informative in everyday practice, and it identifies the subgroup that most urgently demands therapeutic innovation, namely functional CMD. It also reminds us that progress in INOCA will not come solely from refining diagnostic thresholds or classifying endotypes, but from a sustained commitment to developing treatments that address the unique biology of these disorders. As diagnostic capabilities evolve and the evidence base expands, the goal is no longer simply to explain angina in the absence of obstructive CAD, but to meaningfully improve the lived experience of these patients. Studies such as this one bring us closer to that future, while also highlighting how much work remains.
Ongoing trials such as WARRIOR (NCT03417388), PRIZE (NCT04097314), and CorCTCA (NCT03477890) will help clarify whether intensified antiatherosclerotic regimens, inosine monophosphate dehydrogenase inhibition, or novel endothelial targeted strategies can alter the disease trajectory in these patients. Until such data are available, however, the management of functional MVD remains anchored in lifestyle optimization and empiric combinations of antianginal therapies, offering hope rather than assurance of clinical improvement.
FUNDINGNone.
CONFLICTS OF INTERESTH.M. García-García has received research grants from Medtronic, Biotronik/Teleflex, Abbott, Neovasc, CorFlow, Philips, Chiesi, Boston Scientific, Cordis, SpectraWave, AngioWave, Medis, Elixir, Terumo, and MedHub. He has also received consulting fees and honoraria from Boston Scientific, Medis, Abbott, Elixir, Biotronik/Teleflex, and Terumo. All other authors report no conflicts of interest.