


Angina or myocardial ischemia with nonobstructive coronary artery disease (ANOCA/INOCA) is associated with an elevated risk of adverse outcomes. This study aimed to evaluate the prognosis of patients with ANOCA/INOCA who received tailored therapy according to their endotype, as defined by invasive coronary function testing (CFT).
MethodsThis prospective, multicenter observational study included ANOCA/INOCA patients who underwent an invasive CFT. The primary outcome was a composite of total episodes of myocardial infarction, emergency department visits for chest pain, or hospital admissions for angina or heart failure that occurred during a long-term follow-up. Negative binomial regression was used to assess the association between endotypes and total events, with risk estimates expressed as incidence rate ratios (IRR).
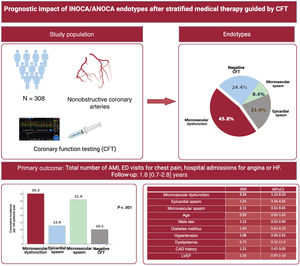
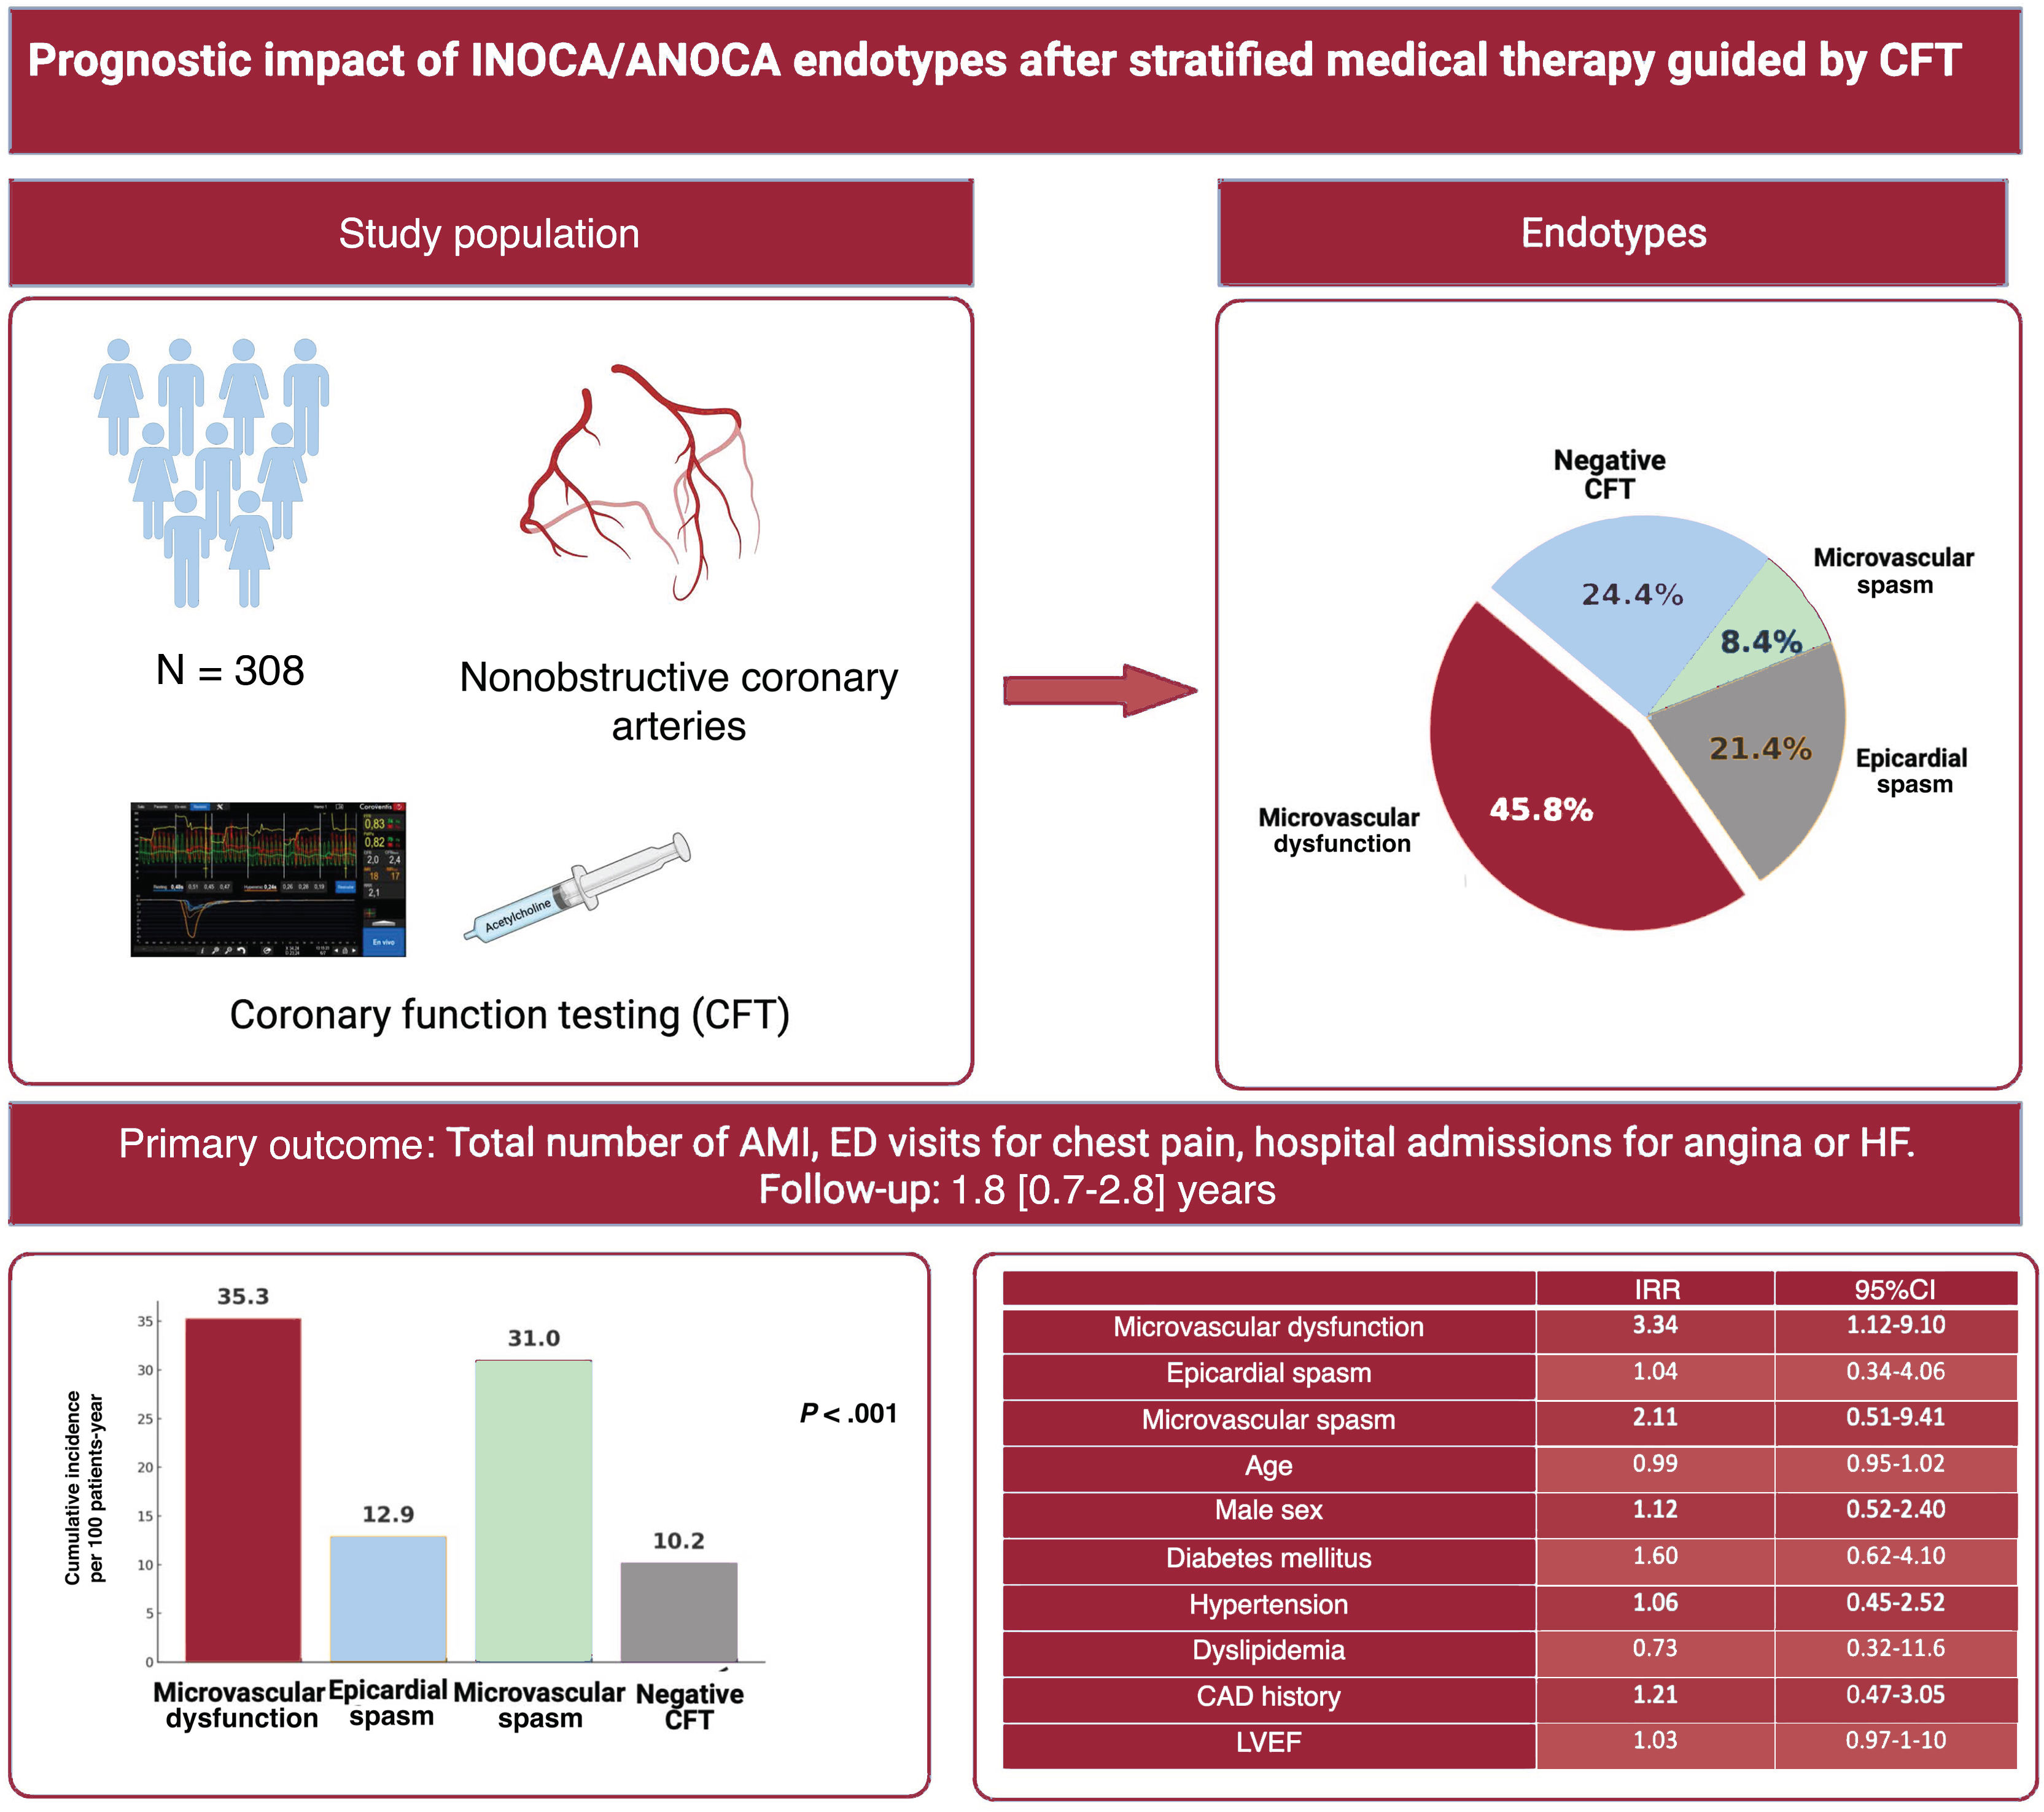
ResultsFrom January 2020 to November 2023, a total of 308 patients were enrolled. Patients were stratified into 4 endotypes: microvascular dysfunction (n=141), epicardial spasm (n=66), microvascular spasm (n=26), or negative-CFT (n=75). At a median follow-up of 1.8 years, the incidence rates of the composite outcome per 100 patient-years were 35.3, 12.9, 31.0, and 10.2 in microvascular dysfunction, epicardial spasm, microvascular spasm, and negative-CFT endotypes, respectively (P <.001). After multivariable adjustment, microvascular dysfunction emerged as the only independent predictor of the composite outcome (IRR, 3.24; 95%CI, 1.12-9.05; P=.029).
ConclusionsDespite tailored medical therapy, ANOCA/INOCA endotype classification revealed significant prognostic differences, with microvascular dysfunction being the endotype associated with the highest burden of recurrent events.
Keywords
Abbreviations
Chronic coronary syndrome encompasses a heterogeneous spectrum of myocardial ischemia presentations, reflecting the dynamic continuum of coronary vascular function, which involves both the epicardial arteries and the coronary microcirculation.1
This concept challenges the traditional paradigm that flow-limiting epicardial disease is the sole driver of myocardial ischemia, as approximately 40% to 50% of the patients with suspected ischemia who undergo invasive coronary angiography do not exhibit obstructive disease in any epicardial artery.2 This sizable subgroup, defined as angina or myocardial ischemia with nonobstructive coronary arteries (ANOCA/INOCA), is associated with reduced quality of life and places a substantial burden on health care systems.3–5
However, ANOCA/INOCA represents a highly heterogeneous condition from a pathophysiological and prognostic point of view.6 The predominant mechanisms underlying ischemia in these patients include microvascular dysfunction (MVD) and coronary vasomotor abnormalities, which lead to impaired vasodilatory capacity and reduced myocardial blood supply. Coronary function testing (CFT) facilitates the classification of ANOCA/INOCA into distinct endotypes by assessing both endothelium-independent and endothelium-dependent pathways of coronary vascular function. The CorMicA trial showed that a stratified medical approach guided by invasive CFT significantly improved angina symptoms and quality of life in INOCA patients.7 However, the prognostic implications of the various ANOCA/INOCA endotypes remain poorly described. Therefore, this study aimed to assess the long-term prognosis of ANOCA/INOCA patients, classified by invasive CFT, which enables stratified medical therapy.
METHODSStudy designThis was a prospective, investigator-initiated, multicenter study conducted in 3 tertiary referral centers between January 2020 and November 2023. Consecutive patients undergoing invasive coronary angiography and comprehensive CFT were prospectively included. All patients provided written informed consent.
The study was conducted in accordance with the recommendations of the Declaration of Helsinki on clinical research and was approved by the referring ethics committee (Hospital General Universitario de Valencia, Spain) and endorsed by all participating institutions.
Patient populationOur inclusion criteria were patients with chronic coronary syndrome referred for invasive coronary angiography due to anginal symptoms, either with suspected ischemia or documented ischemia on prior noninvasive testing, who had nonobstructive coronary artery disease and underwent invasive CFT as part of their diagnostic work-up.
Nonobstructive coronary artery disease was defined as normal coronary arteries or the presence of ≤ 50% stenosis of the coronary artery diameter measured by quantitative coronary analysis. Coronary stenosis> 50% was also included if a negative functional assessment was obtained (confirmed by pressure-based indices as appropriate, defined as a fractional flow reserve> 0.80 or a nonhyperemic pressure ratio> 0.89). In vessels with functionally obstructive coronary artery disease, defined as a a fractional flow reserve of ≤ 0.80 or a nonhyperemic pressure ratio <0.89, percutaneous coronary intervention was recommended according to clinical practice guidelines at the time of the procedure.1,8 The final decision about revascularization was left to the operator's discretion.
Exclusion criteria included the presence of acute coronary syndromes, of at least a moderate valvopathy, any structural cardiomyopathy or elevation of cardiac necrosis markers. We also excluded patients diagnosed with combined endotypes after invasive CFT (n=38), given that overlapping mechanisms and heterogeneous clinical course preclude accurate prognostic stratification.
Study proceduresInvasive coronary angiography was performed using standard techniques, with the radial approach being the preferred route of access in 301 patients (98%). Following diagnostic invasive coronary angiography and exclusion of obstructive coronary artery disease, a CFT was performed during the same procedure.
Invasive CFTPatients were instructed not to take either caffeine or antianginal medications within 12hours before the invasive coronary angiography. Endothelium-independent vasodilation was assessed using bolus thermodilution and the Coroventis system (Coroflow, Sweden). A temperature-pressure wire (PressureWire X, Abbott Vascular, United States) was advanced distally into the coronary target vessel after pressure equalization and intracoronary nitrate administration (100-200μg). The recommended target vessel was the left anterior descending coronary artery. Baseline mean transit time (Tmn) was calculated as the average of 3 measurements obtained after injecting 4mL of room-temperature saline. Subsequently, intravenous adenosine (140μg/kg/min) was administered as a vasodilatory agent to induce hyperemia. A waiting period of at least 3minutes was observed to ensure adequate hyperemia before obtaining hyperemic Tmn. The thermodilution process was repeated 3 times under hyperemic conditions, and the average hyperemic Tmn was calculated from these readings. Coronary flow reserve (CFR) was automatically calculated as the ratio of hyperemic Tmn to baseline Tmn. The index of microcirculatory resistance was determined by multiplying hyperemic distal coronary pressure by Tmn during hyperemia. For this study, normal thresholds were defined as CFR ≥ 2.5 and IMR <25, based on prior studies.1,9
Coronary endothelial function was assessed using the acetylcholine (Ach) test, which involved graded doses infused through the guiding catheter. The protocol for Ach administration consisted of progressive doses of 2μg, 20μg, and 100μg in the left coronary artery (reaching 200μg in selected cases). In all cases, Ach testing was performed in the left coronary artery. Pre-Ach and post-Ach cine images were obtained for quantitative coronary analysis.
The protocol was standardized, with thermodilution measurements systematically performed prior to Ach administration.
Endotypes definitionBased on the results of invasive CFT, patients were classified into 4 endotypes, following the EAPCI Expert Consensus Document6 and COVADIS criteria10,11:
- 1.
MVD: defined as a CFR <2.5 and/or an index of microvascular resistance (IMR) ≥ 25.
- 2.
Epicardial spasm: defined as a focal or diffuse epicardial coronary diameter constriction ≥ 90% during the Ach test with reproduction of recognizable angina symptoms and ischemic electrocardiogram changes (ST-segment depression or elevation> 0.1mV) in at least 2 contiguous leads.
- 3.
Microvascular spasm (MS): diagnosed when recognizable angina symptoms were reproduced with ischemic electrocardiogram changes in the absence or <90% diameter constriction during the Ach test.
- 4.
Negative CFT (N-CFT): characterized by the absence of any coronary dysfunction, with normal findings in both endothelium-independent pathways (CFR ≥ 2.5 and IMR <25) and endothelium-dependent pathways (normal ACh test).
Patients with MVD were also subclassified into 3 subendotypes according to CFR and IMR values: functional MVD: CFR <2.5 and IMR <25; structural MVD: CFR <2.5 and IMR ≥ 25; and isolated high IMR: CFR ≥ 2.5 and IMR ≥ 25.
After classification into endotypes, the initiation of targeted medical therapy was guided by current clinical guidelines.1,6
OutcomesThe primary outcome was a composite of the total number of acute myocardial infarctions (AMI), emergency department visits for chest pain, hospital admissions for angina, or heart failure.
AMI was defined according to the fourth universal definition and was subclassified according to type.12 We considered visits to the emergency department for acute chest pain, if a coronary origin was suspected and the patient was assessed by a cardiologist. Admission for heart failure was defined as a hospital admission of> 24hours with any of the following signs and/or symptoms: worsening breathlessness, fatigue, fluid overload, pulmonary edema, elevated venous pressure, and requirement of intravenous diuretics or inotropes. Confirmation of heart failure according to local expert judgment was required for the event to be classified as admission for heart failure.
All events were identified and quantified by reviewing patients’ health care records, including hospital admissions and emergency room visits. Researchers in charge of endpoint adjudication were blinded to the exposures.
Statistical analysisContinuous variables are presented as the mean±standard deviation according to their distribution, which were checked by the Kolmogorov-Smirnov test and visual inspection of Q-Q plots. All categorical variables are presented as numbers and relative frequencies (percentages). Continuous variables were compared based on a 1-way analysis of variance, and dichotomous variables were compared using chi-square tests or the Fisher exact tests.
A descriptive analysis of recurrent events was performed by counting the number of events during the entire follow-up. Crude incidence rates (expressed as the number of events per 100 person-year) were calculated for each outcome among INOCA endotypes. Negative binomial regression evaluated the association among different INOCA endotypes and the number of total events during the entire follow-up. Because an increase in adverse events is thought to be associated with an increased risk of subsequent death, it has been suggested that any analysis of recurrent intermediate endpoints should also account for death as a terminal event. Thus, coefficients from this method were estimated by accounting for the positive correlation between the recurrent outcome and death as a terminal event by linking the 2 simultaneous equations. Covariate selection was performed based on previous medical knowledge. The covariates included in the recurrent events final models were: age, sex, hypertension, diabetes mellitus, dyslipidemia, previous known coronary artery disease, and left ventricular ejection fraction.
A 2-sided P-value of <.05 was considered to be statistically significant for all analyses. All survival analyses were performed using STATA 15.1 (StataCorp. 2015. Stata Statistical Software: Release 14.1. College Station, StataCorp LP, United States). The ‘Bivcnto’ Stata module was used in the multivariable regression models for bivariate count outcomes.
RESULTSBaseline characteristicsThis multicenter study enrolled 308 patients. The baseline clinical characteristics of the study population are summarized in table 1. The median age was 64 [57.0-71.5] years, and 53.2% were women. Cardiovascular risk factors were common: 59.7% had hypertension, 61.4% dyslipidemia, 23.4% diabetes, and 18.8% were current smokers. A history of coronary artery disease was present in 22.4% of patients, defined as previous AMI or unstable angina, and 18.5% had undergone previous percutaneous coronary interventions. No cases of prior surgical revascularization were reported. A total of 14.0% of patients had previously undergone 2 or more invasive coronary angiography procedures with no evidence of obstructive coronary artery disease.
Patients’ baseline clinical characteristics
| Variable | Overall(n=308) | Negative CFT(n=75) | Microvascular dysfunction(n=141) | Epicardial spasm(n=66) | Microvascular spasm(n=26) | p |
|---|---|---|---|---|---|---|
| Characteristics | ||||||
| Age, y | 64 (57-71.5) | 64 (55-71) | 65 (58-70) | 65(57-72) | 73(60-77) | .019 |
| Female sex | 164 (53.3) | 42 (56) | 71 (50.4) | 32 (48.5) | 19 (73.1) | .144 |
| Hypertension | 184 (59.7) | 43 (57.3) | 99 (70.2) | 33 (50.0) | 9 (34.6) | .001 |
| Dyslipidaemia | 189 (61.4) | 47 (62.7) | 91 (64.5) | 38 (57.6) | 13 (50.0) | .481 |
| Diabetes mellitus | 72 (23.4) | 20 (26.7) | 36 (25.5) | 10 (15.1) | 6 (23.1) | .346 |
| Current smoker | 58 (18.8) | 15 (20.0) | 24 (17.0) | 16 (24.2) | 3 (11.5) | .468 |
| Previous smoker | 66 (21.4) | 13 (17.3) | 34 (24.1) | 15 (22.7) | 4 (15.4) | .576 |
| Atrial fibrillation | 21 (7.3) | 3 (4.6) | 14 (10.8) | 1 (1.5) | 3 (11.5) | .074 |
| Peripheral artery disease | 7 (2.3) | 1 (1.3) | 3 (2.1) | 1 (1.5) | 2 (7.7) | .410 |
| CAD history | 69 (22.4) | 22 (29.3) | 31 (21.9) | 12 (18.2) | 4 (15.4) | .321 |
| Previous PCI | 57 (18.5) | 20 (26.7) | 23 (16.3) | 10 (15.1) | 4 (15.4) | .219 |
| ≥ 2 prior normal* coronary angiograms | 43 (14.0) | 11 (14.6) | 10 (7.1) | 18 (27.3) | 4 (15.4) | .599 |
| LVEF, % | 60 (59-62.4) | 60 (59-60) | 60 (60-65) | 60 (55-60) | 60 (60-63) | .229 |
| NT-proBNP, pg/mL | 315 [109-1105] | 178 [120-483] | 418 [171-1409] | 339 [106-1117] | 111 [46-1063] | .168 |
| Symptoms | ||||||
| Exertional angina | 178 (57.8) | 39 (52.0) | 81 (57.4) | 38 (57.6) | 20 (77.0) | .360 |
| Rest angina | 128 (41.5) | 27 (36.0) | 59 (41.8) | 28 (42.4) | 14 (53.8) | .400 |
| Coronary function testing | ||||||
| FFR | 0.91±0.6 | 0.92±0.1 | 0.91±0.2 | 0.89±0.3 | 0.93±0.1 | .120 |
| CFR | 2.8 (1.8-3.9) | 3.9 (3.2-5.1) | 1.9 (1.5-2.5) | 3.3 (2.9-4.2) | 4.3 (3.45-5.5) | <.001 |
| IMR | 20 (12-33) | 13.5 (9-19) | 32 (22-45) | 14 (9-17) | 14 (10-18) | <.001 |
| Treatment at discharge | ||||||
| ACEI or ARBs | 157 (51.0) | 35 (46.6) | 77 (54.6) | 33 (50.0) | 12 (46.1) | .630 |
| Beta-blockers | 128 (41.5) | 27 (36.0) | 96 (68.0) | 0 | 5 (19.2) | <.001 |
| Nondihydropyridine CCB | 66 (21.4) | 5 (6.6) | 12 (8.5) | 35 (66.0) | 14 (53.9) | .040 |
| Dihydropyridine CCB | 74 (24.0) | 15 (20.0) | 32 (22.7) | 22 (33.3) | 5 (19.2) | .190 |
| Nitrates | 94 (30.5) | 7 (9.3) | 44 (31.2) | 32 (48.5) | 11 (42.3) | .040 |
| Statins | 242 (78.6) | 61 (81.3) | 114 (84.8) | 48 (72.7) | 19 (73.1) | .630 |
| Ranolazine | 65 (21.1) | 7 (9.3) | 33 (23.4) | 18 (27.3) | 7 (27.0) | .028 |
| Aspirin | 159 (51.6) | 37 (49.3) | 79 (56.0) | 31 (47.0) | 12 (46.1) | .544 |
| ISGLT2i | 30 (9.7) | 7 (9.3) | 15 (10.6) | 5 (7.6) | 3 (11.5) | .921 |
| OACs | 23 (7.5) | 1 (1.3) | 17 (12.0) | 2 (3.0) | 3 (11.5) | .014 |
ACEI, angiotensin-converting enzyme inhibitor; ARB, angiotensin receptor blocker; CAD, coronary artery disease; CCB, calcium channel blockers; CFR, coronary flow reserve; CFT, coronary function testing; FFR, fractional flow reserve; IMR, index of microcirculatory resistance; ISGLT2i, sodium-glucose cotransporter 2 inhibitors; LVEF, left ventricular ejection fraction; NT-proBNP, N-terminal pro-B-type natriuretic peptide; OACs, oral anticoagulants; PCI, percutaneous coronary intervention.
Data are expressed as No. (%), mean±standard deviation or median [interquartile range].
We categorized the study population into 4 endotypes according to CFT results: 75 patients (24.3%) had a N-CFT, 141 (45.8%) showed MVD, 66 (21.4%) ES, and 26 (8.4%) MS. Patients with MS were significantly older and hypertension was more prevalent in the MVD endotype. Although no significant sex differences were found among endotypes, the MS group exhibited the highest proportion of female patients (73.1%), suggesting a potential sex-related pattern that might become statistically significant in a larger cohort. We found no differences in diabetes, dyslipidemia, or smoking among the endotypes. Likewise, there were no significant differences in the rate of prior ischemic cardiomyopathy and left ventricular ejection fraction. The pattern of angina presentation was similar among the endotypes. Overall, 57.8% of patients experienced exertional angina, while 41.5% reported angina at rest.
In all cases, the the vessel evaluated for both thermodilution and Ach testing was the left anterior descending artery. CFT findings revealed no significant differences in a fractional flow reserve values among endotypes. The median CFR and IMR values were 3.9 and 13.5, respectively. Regarding medical treatment, the prescription rate for angiotensin-converting enzyme inhibitors or angiotensin receptor blockers was relatively low (46.6%), whereas statin use was considerably higher, observed in 81.3% of patients. Approximately 50% of patients were on aspirin therapy. Patients with MVD were more frequently treated with beta-blockers (68%), while those with spasm endotypes more commonly received calcium channel blockers and nitrates. Among patients with ES, calcium channel blockers were prescribed in 99.3% of cases. None of the patients received a combination of dihydropyridine and nondihydropyridine agents. Ranolazine was also more frequently used in the treatment of vasomotor disorders. Anticoagulant therapy was more often prescribed in patients with MVD (12%) compared with those with other endotypes. No other significant differences in medical management were observed among endotypes.
Complications related to invasive CFT occurred in 16 patients (5.3%). Minor complications, including onset of atrial fibrillation (n=7) and transient bradyarrhythmias or atrioventricular block (n=8) were experienced in 15 (4.9%) patients. A single major complication was reportedad (an ischemic stroke that developed shortly after the procedure), accounting for 0.3% of the total.
Endotypes and composite outcomeDuring a median follow-up of 1.8 [0.7-2.8] years, a total of 93 combined events were recorded (4 AMI, 77 emergency department visits for chest pain, 11 hospital readmissions due to angina, and 1 admission for heart failure) in 48 patients (15.7%) (table 2). The baseline characteristics of patients with and without events were compared, revealing a significantly higher prevalence of angina at rest in the event group (56.2% vs 38.8%; P=.020), as shown in table S1. No other significant differences were found. Of note, all 4 AMI events met the criteria for myocardial infarction with nonobstructive coronary arteries (MINOCA), showing troponin elevation and ischemic symptoms, but without new obstructive lesions on invasive coronary angiography (table S2). Importantly, none of these events resulted in left ventricular systolic dysfunction. During follow-up, 3 deaths occurred, none of which were of cardiovascular origin. The cumulative incidence of the composite outcome per 100 patient-years was higher in patients with MVD (35.3) and MS (31.0) and lower in those with ES (12.9) and N-CFT (10.2), P=.020. The increased event rates observed in patients with MVD and MS were primarily due to a higher number of emergency department visits for chest pain (25.3, 27.1, 12.9, 8.9 per 100-person-years for MVD, MS, ES, and N-CFT, respectively, P <.001).
Distribution of clinical events according to endotype
| Omnibus | Negative CFT(n=75) | Microvascular dysfunction(n=141) | Epicardial spasm(n=66) | Microvascular spasm(n=26) | P* |
|---|---|---|---|---|---|
| Primary outcome (AMI, admissions for angina or HF and/or ED visits for chest pain) | 9 (12) | 58 (41.1) | 14 (21.2) | 12 (46.1) | .010 |
| AMI | 0 (0) | 4 (2.8) | 0 (0) | 0 (0) | .280 |
| Admissions for angina | 1 (1.3) | 9 (6.4) | 0 (0) | 1 (3.8) | <.001 |
| Admissions for HF | 0 (0) | 1 (0.7) | 0 (0) | 0 (0) | 1 |
| ED visits for chest pain | 8 (10.6) | 44 (31.2) | 14 (21.2) | 11 (42.3) | .016 |
| Noncardiac death | 2 (2.6) | 2 (1.4) | 0 (0) | 0 (0) | .692 |
AMI, acute myocardial infarction; CFT, coronary function test; ED, emergency department; HF, heart failure.
Data are expressed as no. (%).
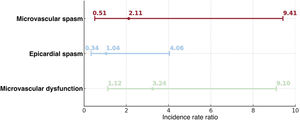
After multivariable adjustment, including age, sex, diabetes, hypertension, dyslipidemia, chronic kidney disease, coronary artery disease history and left ventricle ejection fraction, and when compared to individuals with N-CFT, MVD endotype remained independently associated with an increased risk of composite endpoint, (incidence rate ratios [IRR], 3.24; 95% confidence interval [95%CI], 1.12-9.10; P=.005) (figure 1). ES and MS were not associated with an increased risk, IRR, 1.04; 95%CI, 0.34-4.06 and IRR 2.11; 95%CI, 0.51-9.41 respectively (figure 2).

Central illustration. Prognostic impact of INOCA/ANOCA endotypes after stratified medical therapy guided by CFT. CFT enables endotype classification in ANOCA/INOCA patients. Following tailored medical therapy, a prognostic gradient was observed, with MVD emerging as an independent predictor of adverse outcomes. AMI, acute myocardial infarction; ANOCA, angina with nonobstructive coronary arteries; CAD, coronary artery disease; CFT, coronary function test; ED, emergency department; HF, heart failure; INOCA, ischemia with nonobstructive coronary arteries; LVEF, left ventricular ejection fraction.

The MVD population was further categorized into 3 subendotypes: structural MVD in 71 patients (23.0%), functional MVD in 39 patients (12.6%) and isolated high IMR in 31 patients (10.0%). Patients with functional and structural MVD showed no significant differences in CFR values: 1.7 (1.2-2.1) vs 1.8 (1.5-2.2), respectively; P=.673.
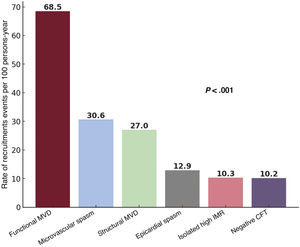
Considering the entire cohort among the 6 predefined coronary endotypes, the highest rate of recurrent events was found in patients with functional MVD (68.5 per 100 patient-years), followed by those with MS and structural MVD (30.6 and 27.0 per 100 patient-years, respectively). The lowest rates were observed in patients with ES (12.9 per 100 patient-years), isolated high IMR (10.3) and N-CFT (10.2), as shown in figure 3.

Crude incidence rates of the composite outcome in MVD subendotypes, negative coronary function tests, microvascular spasm, and epicardial spasm. CFT, coronary function testing; IMR, index of microvasculatory resistance; MVD, microvascular dysfunction. Statistical comparison based on univariable negative binomial regression.
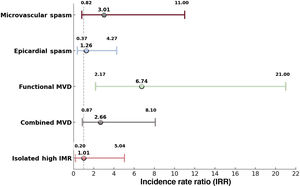
After multivariable adjustment, compared with N-CFT, functional MVD was the only endotype showing an independent association with increased risk IRR, 6.74; 95%CI, 2.17-21.0 (figure 4).

Risk of the composite outcome in MVD subendotypes, microvascular spasm, and epicardial spasm compared with negative coronary function test in the multivariable regression models for bivariate count outcomes. IMR, index of microvasculatory resistance; MVD, microvascular dysfunction.
In the present study, we assessed the long-term prognostic relevance of distinct ANOCA/INOCA endotypes in patients managed with stratified medical therapy guided by invasive CFT. The principal findings were: a) prognosis varied significantly among ANOCA/INOCA endotypes; b) MVD was associated with the poorest long-term outcomes; and c) functional MVD (CFR <2.5 and IMR <25) independently predicted an increased risk of adverse events during follow-up.
The term ANOCA/INOCA encompasses a heterogeneous spectrum of clinical conditions unified by the absence of obstructive coronary artery disease. Despite this common feature, ANOCA/INOCA endotypes differ substantially in their underlying pathophysiological mechanisms, ranging from MVD and vasomotor disorders (ES and MS) to entirely normal coronary physiology (N-CFT).13 A key strength of this study lies in the use of a standardized, protocol-driven CFT, which allowed consistent classification of endotypes based on contemporary recommendations,6–11 thereby enhancing diagnostic accuracy and patient stratification.
INOCA endotypes and risk of the composite outcomeTraditionally, overall ANOCA/INOCA patients have been associated with a high symptom burden, impaired quality of life, and increased use of health care resources.3–5,14 However, most studies assessing prognosis in this population have focused primarily on major adverse cardiovascular events (MACE), such as mortality, AMI, or the need for revascularization. Radico et al.15 reported an incidence of all-cause death and AMI of 0.98 per 100 person-years in a meta-analysis that included 35 039 patients with ANOCA. In contrast, the recurrence rate of angina was substantially higher, reaching 8.24 per 100 person-years. However, this pooled analysis had several limitations, mainly attributed to the heterogeneity of the included patient population. These findings agree with those of a more recent meta-analysis by Odanović et al.,16 which included 54 studies and reported a combined incidence of all-cause death and AMI of 1.0 (95%CI, 0.6-1.4) per 100 person-years.
Our study used a composite outcome that clearly revealed a marked gradient in risk among endotypes. Although emergency department visits for chest pain may be regarded as a soft endpoint, they represent a major source of symptom burden and resource utilization, which is a hallmark of ANOCA/INOCA patients. Patients with MVD exhibited the highest cumulative incidence of the combined event, with a 3-fold increase in event rate compared with those with N-CFT. This was followed by those with MS, who displayed a slightly lower but still elevated incidence. This divergent behavior among ANOCA/INOCA subtypes may reflect the underlying severity of their distinct pathophysiological mechanisms and is also likely influenced by the availability of subtype-specific treatments. The low rate of events in ES patients, with outcomes nearly comparable to those observed in patients with N-CFT, may reflect the benefit of calcium channel blockers as a targeted therapeutic strategy in this subgroup, which were used in 99.3% of these patients. Similar results were observed by Odanović et al.,16 as patients with ES had at least half the combined incidence of MACE compared with those with MVD (1.1 vs 2.5 per 100 person-years). In line with these findings, the study by Seitz et al.,17also reported a very low rate of AMI in both ES and MS, around 0.1% per year. However, MS was an independent predictor of recurrent angina.
Microvascular dysfunction as a predictor of adverse clinical eventsThe association between low CFR and poor outcomes was reported by Pepine et al.,18 in a subanalysis from the WISE study. A CFR less than 2.32 was the best discriminating threshold for adverse outcomes in this cohort of women, with low CFR being an independent predictor of MACE. Subsequently, many studies have evaluated the prognostic impact of abnormal CFR in a broad spectrum of cardiovascular diseases.19 To the best of our knowledge, this is the first study to evaluate long-term clinical outcomes in ANOCA/INOCA patients managed according to their CFT-defined endotype, highlighting the prognostic relevance of stratified therapy based on underlying coronary pathophysiology. In this study, MVD emerged as an independent predictor of the composite outcome, largely driven by emergency visits for chest pain and angina-related rehospitalizations. Ultimately, CFR represents the vasodilatory capacity of the coronary microcirculation. An impaired CFR indicates the inability of the microvasculature to augment epicardial blood flow, which may, in turn, lead to angina. Despite its clinical impact, MVD currently lacks a specific therapeutic target, which may result in recurrent or refractory angina.
Microvascular dysfunction subendotypesThe clinical impact of a reduced CFR was further highlighted when we examined the different endotypes associated with MVD. The current diagnostic criteria for MVD include a CFR <2.5 and/or an IMR ≥ 25. A subclassification into structural (CFR <2.5 and IMR ≥ 25) and functional MVD (CFR <2.5 and IMR <25) has been proposed, emphasizing their different etiological mechanisms.
Structural MVD is considered to reflect architectural alterations in the microvasculature, including capillary rarefaction and arteriolar obliteration, leading to impaired vasodilatory capacity of the microcirculation. In contrast, functional MVD is thought to result from either increased myocardial oxygen demand or dysregulated coronary autoregulation, both of which can lead to higher coronary flow at rest despite a stable myocardial workload and preserved microcirculatory function during maximal vasodilation.20
In this context, Boerhout et al., in the ILIAS registry,21 evaluated the prognostic implications of structural vs functional MVD in a cohort of ANOCA patients. These authors found that an abnormal CFR (< 2.5) was associated with an increased risk of 5-year MACE (all-cause death, AMI, and clinically driven revascularization) (hazard ratio [HR], 2.05; 95%CI, 1.47-2.87; P <.005) and 5-year target vessel failure (TVF) (cardiac death, AMI not attributable to a nontarget vessel) (HR, 2.27; 95%CI, 1.47-3.49; P <.005). However, the microcirculatory parameter IMR was not associated with MACE or TVF at 5 years of follow-up.
In light of this evidence, we classified MVD into 3 subendotypes: structural, functional, and isolated high IMR, aiming to offer a prognostically meaningful framework for the stratification of ANOCA/ INOCA patients. Functional MVD was associated with the greatest burden of recurrent events (68.5 per 100 patient-years), with rates more than twice as high as those observed in MS and structural MVD. Conversely, isolated high IMR demonstrated a rate of recurrent events (10.3 per 100 patient-years) comparable to that of patients with normal coronary physiology (10.2 per 100 patient-years), suggesting a limited prognostic impact. In the multivariable analysis, functional MVD was the only independent predictor of the combined outcome (IRR, 6.8; 95%CI, 1.77-26.4), whereas structural MVD showed a trend toward significance but did not reach statistical significance (IRR, 2.6, 95%CI, 0.8-8.6). These findings reveal that the increased risk observed in patients with abnormal CFR was independent of IMR values, highlighting the prognostic significance of a low CFR. Boerhout et al.21 found that both functional and structural MVD were independent predictors of MACE and TVF at 5 years of follow-up. Conversely, a recent meta-analysis by Al-Gully et al.,22 which included the ILIAS registry, reported that structural MVD was associated with an increased risk of both MACE and all-cause mortality, whereas functional MVD was associated only with MACE. However, it is important to highlight that all-cause mortality was very low overall, averaging around 4% and reported in only 2 of the included studies, which limits the strength of these conclusions. In line with our study, Lee et al.,23also observed that patients with high IMR and low CFR had the poorest prognosis. However, the evaluated outcome in their study was a patient-oriented composite endpoint (death, AMI, and revascularization), and the excess risk was mainly driven by a higher rate of revascularization during follow-up rather than events directly attributable to coronary microvascular dysfunction. This contrasts with our findings, which focused on symptom-driven outcomes.
LimitationsTheis study has several limitations. First, this is an observational study in which hidden bias might be present. Second, CFR and IMR values were assessed exclusively using the bolus thermodilution technique, which may have lower reproducibility. Third, although intravenous adenosine is generally considered to provide reliable maximal hyperemia, the possibility of a suboptimal hyperemic response in some cases cannot be entirely ruled out. This may have led to a misclassification of some patients as having structural MVD, potentially increasing its prevalence and contributing to their relatively favorable prognosis. Fourth, we did not perform physiological evaluations of the right coronary artery or left circumflex coronary artery. Fifth, medical treatment during follow-up was individualized according to symptom persistence at the discretion of each attending physician, potentially introducing bias. Sixth, we did not have data regarding changes in quality of life or symptoms. Seventh, the follow-up period was relatively short (median 1.8 years). A longer follow-up may result in a higher number of clinical events, which could further refine the prognostic differences observed among endotypes. Eighth, we excluded patients with combined endotypes. Although this decision limits the generalizability of our findings, it was intended to enable a clearer evaluation of the prognostic significance of individual mechanisms. Overlapping endotypes may require distinct management strategies and have heterogeneous clinical trajectories that complicate accurate risk stratification. Future studies specifically designed to address this subgroup are warranted. Finally, we did not systematically record the proportion of all patients with nonobstructive coronary disease who underwent angiography but did not receive CFT. This may have introduced a selection bias and limits the representativeness of the included sample.
CONCLUSIONSIn patients with suspected ischemia and nonobstructive coronary arteries, invasive CFT enables classification into distinct ANOCA/INOCA endotypes. In this real-world cohort treated according to CFT-derived diagnoses, endotypes showed different clinical trajectories, with MVD—particularly functional impairment—being associated with the highest burden of recurrent events. These findings highlight the prognostic importance of coronary endotypes under current medical treatment, supporting the clinical usefulness of CFT to guide personalized management.
FUNDINGThe authors received no specific funding for this work.
ETHICAL CONSIDERATIONSThe study protocol was approved by the Consorcio Hospital General Universtario de Valencia ethics committee on human research and complies with the 1975 Declaration of Helsinki guidelines. All participants provided written informed consent for the publication of their case. SAGER guidelines were followed to avoid potential sex/gender bias.
STATEMENT ON THE USE OF ARTIFICIAL INTELLIGENCENo artificial intelligence was used in the conduct, analysis, or drafting of this manuscript.
AUTHORS’ CONTRIBUTIONSEach author contributed significantly to the submitted work. Substantial contributions to the conception or design of the work; or the acquisition, analysis, or interpretation of data: E. Rumiz, G. Fuertes, A. Pérez, E. Valero, G. Llopis, J. Núñez, J. Escaned. Drafting the work or revising it critically for important intellectual content: E. Rumiz, G. Fuertes, A. Pérez, G. Llopis, L. Cerdán, P. Vadillo, A. Carrión, I. Ezpeleta, C. Buisán, S. Cardona, E. Valero, J. Escaned, J. Núñez. All authors approved the final version to be published. All authors agreed to be accountable for all aspects of the work in ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
CONFLICTS OF INTERESTNone.
- –
ANOCA/INOCA encompasses a spectrum of pathophysiological mechanisms that cause myocardial ischemia without obstructive coronary artery disease.
- –
Patients with ANOCA/INOCA often show persistent angina and require repeated health care visits despite having nonobstructive coronary anatomy.
- –
CFT enables the classification of patients into functional endotypes, allowing a tailored medical treatment aimed at improving angina symptoms and quality of life.
- –
Stratification of ANOCA/INOCA patients based on invasive CFT results allows the identification of distinct endotypes with different clinical outcomes, even after tailored medical therapy.
- –
ES showed the lowest event rate, whereas CMD—particularly functional CMD—was associated with the highest burden of adverse events.
- –
These findings highlight a prognostic gradient among ANOCA/INOCA endotypes despite recommended treatment, supporting the role of CFT in selected patients to refine risk assessment and facilitate personalized management.
The authors guarantee that the following researchers are responsible for the data published in this study: Eva Rumiz, Consorcio Hospital General Universitario de Valencia, Valencia; Georgina Fuertes, Hospital Universitario Miguel Servet, Zaragoza; Ainhoa Pérez, Hospital Lozano Blesa, Zaragoza; Julio Núñez, Hospital Clínico Universitario de Valencia, Valencia; Javier Escaned, Hospital Clínico San Carlos, Madrid.
Supplementary data associated with this article can be found in the online version, at https://doi.org/10.1016/j.rec.2025.11.012